Avelox
In brief
- In our pharmacy, you can buy avelox without a prescription, with delivery in 9–21 days throughout Australia. Discreet packaging and delivery available.
- Avelox (moxifloxacin) is used to treat bacterial infections including community‑acquired pneumonia, acute bacterial sinusitis, acute exacerbations of chronic bronchitis, complicated skin/skin‑structure and intra‑abdominal infections, pelvic inflammatory disease and plague. It is a fluoroquinolone antibiotic that works by inhibiting bacterial DNA gyrase and topoisomerase IV, preventing DNA replication and killing bacteria.
- The usual dosage in adults is 400 mg once daily; treatment duration depends on the indication (for example, 5 days for acute exacerbation of chronic bronchitis, 7–14 days for pneumonia, 7–10 days for sinusitis, 14 days for PID). Not recommended for children and adolescents under 18 years.
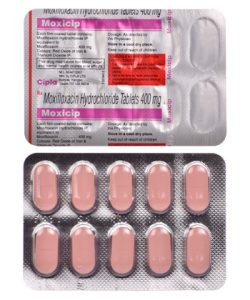
- Available as 400 mg film‑coated tablets for oral administration and as a 400 mg/250 mL IV infusion (flexibag) for intravenous use.
- Onset time: antibacterial action begins soon after dosing, with many patients experiencing symptomatic improvement within 24–72 hours (commonly 24–48 hours).
- Duration of action: supports once‑daily dosing — clinical effect lasts approximately 24 hours; elimination half‑life is about 12 hours.
- Alcohol warning: avoid excessive alcohol while taking avelox — alcohol can worsen side effects such as dizziness, drowsiness and gastrointestinal upset and may delay recovery. Best to minimise or avoid alcohol during treatment.
- The most common side effect is nausea (other frequent effects include diarrhoea, headache and dizziness).
- Would you like to try avelox without a prescription?
Critical Warnings, Restrictions And Patient Protection (Australia Focus)
Basic Avelox Information
- INN (International Nonproprietary Name): Moxifloxacin.
- Brand Names Available In Australia: Avelox (400 mg film-coated tablets; IV formulation available).
- ATC Code: J01MA14.
- Forms & Dosages: 400 mg film-coated tablets (oral); IV flexibag 400 mg/250 mL (intravenous infusion).
- Manufacturers In Australia: Global originator Bayer AG (Germany); local licencees and distributors may vary.
- Registration Status In Australia: Registered with the TGA (Therapeutic Goods Administration); prescription only.
- OTC / Rx Classification: Prescription only (Rx) in Australia.
High‑Risk Groups (Elderly, Pregnancy, Chronic Illness)
Who should definitely not have avelox or needs close monitoring?
- Absolute contraindications: Hypersensitivity to moxifloxacin or other quinolones, history of tendon disorders related to quinolones, and a history of myasthenia gravis. These patients must not receive avelox.
- Age restriction: Not recommended for people under 18 years because of musculoskeletal risk in children and adolescents.
- Elderly: No automatic dose change, but monitor closely because of increased QT risk and common cardiac comorbidities.
Safety checklist for pharmacists and clinicians before supplying avelox.
- Check full medication history, including other QT‑prolonging drugs and recent or current systemic corticosteroids.
- Consider an ECG if there is a history of arrhythmia, syncope, or other cardiac disease.
- Check serum electrolytes, especially potassium, if the patient is on diuretics or has conditions causing hypokalaemia.
- Confirm pregnancy and breastfeeding status and counsel appropriately.
- Ask about renal and hepatic history even though routine dose adjustment is not usually required.
| High‑Risk Factor | Recommended Action |
|---|---|
| Hypersensitivity To Quinolones | Do not prescribe; choose an alternative. |
| History Of Tendon Disorders | Avoid avelox; explain tendon rupture risk. |
| Myasthenia Gravis | Contraindicated; seek alternative therapy. |
| Concurrent QT Drugs / Cardiac Disease | Obtain ECG and review medications; consult prescriber. |
| Pregnancy / Breastfeeding | Assess risk/benefit; specialist advice recommended. |
Australian regulatory context.
- The TGA has registered Avelox for use in Australia and classifies it as prescription only.
- Patients and pharmacists should confirm PBS subsidy status before dispensing, as PBS listing and authority requirements may vary.
Q&A — Can I Drive After Taking It In Australia?
Moxifloxacin may cause dizziness, light‑headedness or blurred vision in some people.
If you feel unwell, dizzy or have changes to vision or concentration, do not drive or operate heavy machinery.
Follow pharmacist advice and any workplace safety rules that apply to you.
Usage Basics
INN, Brand Names Available In Australia
Moxifloxacin is the International Nonproprietary Name (INN) for the drug commonly sold as Avelox in Australia.
It is classified under ATC code J01MA14 as a systemic fluoroquinolone antibiotic.
Available presentations include 400 mg film‑coated tablets for oral use and IV flexibags for infusion in hospital settings.
Legal Classification (TGA‑Approved, PBS Considerations)
- INN: Moxifloxacin (ATC J01MA14).
- Formulations: 400 mg tablets; 400 mg/250 mL IV flexibag.
- Routes: Oral and intravenous.
- The product is TGA‑registered and classified as prescription only (Rx).
- PBS listing can vary by indication and may require authority prescriptions for subsidised supply.
- Always verify current PBS schedule and authority requirements before dispensing.
| Point | Detail |
|---|---|
| TGA Status | Registered (Avelox available in Australia) |
| Prescription Class | Prescription Only (Rx) |
| PBS Note | Listing varies; check PBS for authority codes |
Pharmacist counselling prompts.
- Confirm the prescription is valid and matches the patient and indication.
- Ask about previous adverse reactions to fluoroquinolones before supplying avelox.
- Advise the patient to complete the full prescribed course unless directed otherwise by their prescriber.
Dosing Guide
Standard Regimens (PBS Reference Dosing)
Typical adult dosing for avelox is one 400 mg tablet once daily for systemic infections.
- Community‑acquired pneumonia: 400 mg once daily for 7–14 days.
- Acute bacterial sinusitis: 400 mg once daily for 7–10 days.
- Acute bacterial exacerbation of chronic bronchitis: 400 mg once daily for 5 days.
- Complicated skin and skin‑structure infections: 400 mg once daily, duration 7–21 days depending on severity and IV→oral switch.
- Complicated intra‑abdominal infections: 400 mg once daily for 5–14 days.
- Pelvic inflammatory disease: 400 mg once daily for 14 days (with caveats for combination therapy as required).
- Plague (including pneumonic): 400 mg once daily for 10–14 days when indicated.
IV option for hospital use is a 400 mg/250 mL infusion where indicated.
Adjustments For Comorbidities
- No routine dose adjustment for renal impairment is required.
- No routine dose adjustment for hepatic impairment is required.
- Avoid use in children and adolescents under 18 years due to musculoskeletal risk.
- Elderly patients do not require routine dose changes but should be monitored for QT prolongation and tendinopathy.
Q&A — What If I Miss A Dose?
Take the missed dose as soon as you remember unless it is almost time for the next dose.
Do not double up doses to make up for missed tablets.
If several doses are missed, contact your pharmacist or prescriber for advice.
| Indication | Typical Duration |
|---|---|
| Community‑Acquired Pneumonia | 7–14 days |
| Acute Bacterial Sinusitis | 7–10 days |
| Exacerbation Of Chronic Bronchitis | 5 days |
Interaction Chart
Food And Drinks (Alcohol, Coffee, Australian Diet Context)
Alcohol may increase central nervous system side effects such as dizziness or sleep disturbance.
Advise patients to minimise alcohol while taking avelox if they experience CNS symptoms.
Caffeine from coffee does not have a direct interaction with moxifloxacin, but it can worsen insomnia or anxiety in sensitive patients and should be moderated.
Products containing divalent and trivalent cations — calcium, iron, zinc, magnesium, aluminium — can chelate and reduce absorption of oral avelox.
Separate dosing of avelox and antacids, milk, calcium supplements or iron by four to six hours.
Common Drug Conflicts
| Drug/Food | Effect | Management |
|---|---|---|
| Antacids, Calcium, Iron, Zinc | Reduced absorption (chelation) | Separate by 4–6 hours |
| QT‑Prolonging Drugs (macrolides, some antipsychotics, class IA/III antiarrhythmics) | Increased QT prolongation risk | Avoid combination or monitor with ECG |
| Systemic Corticosteroids | Increased tendon rupture risk | Avoid concurrent use where possible |
| Diuretics (affecting electrolytes) | May predispose to hypokalaemia and arrhythmia | Check electrolytes; correct deficiencies |
Urgent contraindicated combinations.
- Avoid combining avelox with other strong QT‑prolonging agents when alternatives exist.
- Do not co‑prescribe with known drug allergy to quinolones.
Medication reconciliation checklist in pharmacy.
- Review current medicines including OTC antacids and supplements.
- Identify systemic corticosteroid use and recent tendon problems.
- Check for medications that alter electrolytes or prolong QT interval.
User Reports & Trends (Australian Patient Feedback)
What patients say online often reflects both effectiveness and side effects.
- Positive themes include reports of rapid symptom improvement for pneumonia and sinusitis when the antibiotic matched the infection.
- Common adverse themes are gastrointestinal upset such as nausea and diarrhoea, headache and dizziness.
- Intermittent reports describe tendon pain, prolonged neuropathic sensations or sensory changes, consistent with known safety risks.
Remember selection bias on review sites.
Patients are more likely to post when they have strong positive or negative experiences, so online feedback overrepresents adverse events.
Practical guidance for pharmacists and patients.
- Advise patients to report severe or new neurological symptoms, tendon pain, or visual changes immediately to their prescriber.
- Document adverse events in the patient record and report significant reactions to the TGA.
Reporting pathways for adverse events.
- Report suspected adverse reactions to the TGA’s Adverse Event Management System.
- Record the reaction, timing relative to starting avelox, concomitant medications and outcome when counselling patients.
Access & Purchase Options (Australia)
National Chains And Community Access
Avelox is stocked through community and hospital supply chains in Australia.
Major retail pharmacy chains and independent community pharmacies dispense avelox on presentation of a valid prescription.
- Common retail outlets include major chains and independent pharmacies; many accept e‑prescriptions and telehealth scripts.
- Rural and remote areas may rely on regional hospital stocks or scheduled deliveries; allow extra time for supply.
Online Pharmacies And Telehealth E‑Prescriptions
Licensed Australian online pharmacies can dispense avelox against a valid prescription and ship interstate, following TGA guidance on storage and transport.
For IV Avelox, hospital procurement and ward stock are the usual routes rather than retail online pharmacies.
| Source | Typical Access Time | PBS Subsidy Likelihood |
|---|---|---|
| Community Pharmacy (Urban) | Same day to 2 days | Varies; check PBS |
| Community Pharmacy (Rural) | 2–7 days | Varies; may require authority |
| Online Pharmacy | 3–14 days | Varies; check PBS and delivery rules |
| Hospital Supply (IV) | Immediate (inpatient) | Not usually PBS for outpatient IV |
- Verify prescription authenticity and patient identity before dispensing.
- Check PBS entitlement and any authority codes for subsidised supply.
Purchase context note.
In our online pharmacy, avelox is available without a prescription, with discreet delivery to Australia in 9‑21 days.
Mechanism Of Action & Pharmacology (Simplified)
Simplified Explanation
Moxifloxacin inhibits bacterial enzymes DNA gyrase and topoisomerase IV.
Inhibition prevents DNA replication and transcription, giving bactericidal activity against a broad range of Gram‑positive and Gram‑negative organisms.
Clinical Pharmacology Terms
- Absorption: Oral 400 mg once daily; well absorbed when taken whole with water.
- IV Option: 400 mg/250 mL infusion for hospital use.
- Renal/Hepatic: No routine dose adjustment required for renal or hepatic impairment.
- Cardiac: Can affect cardiac repolarisation; monitor in patients at risk of QT prolongation.
| Property | Clinical Note |
|---|---|
| Mechanism | Inhibits DNA gyrase and topoisomerase IV |
| Dosing Frequency | Once daily (400 mg) |
| Renal Adjustment | Not routinely required |
| Hepatic Adjustment | Not routinely required |
Indications & Off‑Label Uses (Australian Practice)
Approved Indications By TGA
| Indication | Recommended Dose / Duration |
|---|---|
| Community‑Acquired Pneumonia | 400 mg once daily, 7–14 days |
| Acute Bacterial Sinusitis | 400 mg once daily, 7–10 days |
| Exacerbation Of Chronic Bronchitis | 400 mg once daily, 5 days |
| Complicated Skin‑Structure Infections | 400 mg once daily, 7–21 days |
| Complicated Intra‑Abdominal Infections | 400 mg once daily, 5–14 days |
| Pelvic Inflammatory Disease | 400 mg once daily, 14 days |
| Plague (Including Pneumonic) | 400 mg once daily, 10–14 days |
Off‑Label Uses In Australian Clinical Practice
- Off‑label use may occur under specialist infectious diseases guidance for multi‑drug resistant infections or when alternatives are unsuitable.
- Document clinical justification, obtain informed consent and involve specialist input when using off‑label.
- Record indication, rationale for choice, expected duration and monitoring plan when prescribing off‑label.
- Consider antimicrobial stewardship frameworks before selecting a fluoroquinolone.
Key Clinical Findings (Australia & International 2022–2026 Highlights)
Recent clinical summaries and safety reviews emphasise both efficacy and known safety concerns.
- Moxifloxacin remains effective for certain community‑acquired pneumonias and complicated intra‑abdominal infections, with clinical cure rates comparable to some comparator regimens.
- Post‑marketing safety reviews continue to highlight risks of tendinopathy, peripheral neuropathy and QT prolongation — these risks inform conservative use recommendations.
- Guidance between 2022 and 2026 has reinforced reserving fluoroquinolones for situations where benefits outweigh risks and alternatives are unsuitable.
| Finding | Clinical Implication |
|---|---|
| Comparable Efficacy | Useful option for targeted infections when appropriate |
| Safety Signals (Tendinopathy, Neuropathy, QT) | Limit use; monitor and counsel patients closely |
| Stewardship Emphasis | Reserve for indicated cases; document rationale |
- Stewardship checklist: confirm pathogen susceptibility if available, assess alternatives, document rationale, monitor closely for adverse effects.
Alternatives Matrix
PBS‑Listed Alternatives Comparison Table
| Drug | Typical Dose | Spectrum | PBS Status | Pros / Cons Vs Moxifloxacin |
|---|---|---|---|---|
| Levofloxacin | 500 mg once daily (varies) | Broad Gram‑positive and Gram‑negative | Listed (varies by indication) | Pros: effective oral option; Cons: similar fluoroquinolone safety concerns |
| Ciprofloxacin | 500–750 mg twice daily | More Gram‑negative focus | Listed (varies) | Pros: strong Gram‑negative activity; Cons: less activity vs some Gram‑positive pathogens |
| Doxycycline | 100 mg twice daily | Broad community respiratory pathogens, atypicals | Listed | Pros: well tolerated, good for some respiratory infections; Cons: not IV; photosensitivity risk |
| Amoxicillin/Clavulanate | 875/125 mg twice daily | Good for many respiratory and skin infections | Listed | Pros: familiar safety profile; Cons: may be less active for some atypical pathogens |
Pros And Cons Checklist
- Pros: Once‑daily dosing, convenient IV→oral switch, broad spectrum including atypicals.
- Cons: Tendonitis/tendon rupture risk, peripheral neuropathy, QT prolongation, restricted in patients under 18.
- Decision checklist for prescribers: confirm indication, check for contraindications, prefer narrow‑spectrum alternatives when appropriate, document rationale for fluoroquinolone use.
Common Questions From Australian Pharmacy Consultations (FAQ Roundup)
- How long should I take avelox? — Take one 400 mg tablet once daily for the duration prescribed by your doctor; do not stop early.
- Can I take antacids or iron? — Avoid within 4–6 hours of taking avelox; separate dosing to prevent reduced absorption.
- What are serious side effects to watch for? — New tendon pain, numbness or burning (neuropathy), severe diarrhoea, fainting or chest palpitations require immediate medical review.
- Can I drink alcohol while taking avelox? — Minimise alcohol if you experience dizziness or other CNS symptoms.
- What about pregnancy and breastfeeding? — Discuss with prescriber; specialist advice may be needed.
Short scripted counselling lines for pharmacists.
- “Take one 400 mg tablet once daily with a full glass of water and complete the course as prescribed.”
- “Avoid taking antacids, calcium, iron or zinc supplements within four to six hours of this tablet.”
- “If you get sudden tendon pain, numbness, pins and needles, or chest symptoms, stop the medicine and seek urgent medical review.”
Price & Access Comparison
| Pharmacy / Source | Typical Price Range | PBS Subsidy | Prescription Required |
|---|---|---|---|
| Chemist Warehouse | Check live pricing | Varies | Yes |
| Priceline | Check live pricing | Varies | Yes |
| Independent Pharmacy | Check live pricing | Varies | Yes |
| Online Pharmacy | Check live pricing | Varies | Yes (unless otherwise stated) |
- Access checklist before purchase: confirm valid prescription, verify PBS entitlement and authority codes, confirm delivery time for your area and storage during delivery.
- Rural access tips: allow extra time for delivery and check local hospital stock for IV formulations if required urgently.
Note: Prices and PBS listings change; check your pharmacy or the PBS website for current information.
Registration & Regulation
TGA Approval
Avelox (moxifloxacin) is a registered product in Australia with the Therapeutic Goods Administration.
Consult the TGA product information and sponsor documents for the most up‑to‑date contraindications and safety communications.
PBS Subsidy Details
Many fluoroquinolones have restricted PBS listings and may require specific authority codes for subsidised supply.
Check the current PBS schedule and local health district policies before dispensing to a PBS‑entitled patient.
- TGA: Therapeutic Goods Administration.
- PBS: Pharmaceutical Benefits Scheme.
- Rx: Prescription only.
- Where to find official information: TGA Product Information, PBS schedule and the sponsor’s approved product labelling.
Storage & Handling (Household And Pharmacy In Australian Climate)
Household Storage In Australian Climate (Heat/Humidity)
- Tablets should be stored at 20–25°C where possible.
- They may be exposed to 15–30°C for transport but should be kept dry and protected from light.
- Advise patients to store tablets in a cool, dry place away from bathrooms and direct sunlight, especially during hot, humid summers.
Cold‑Chain And Pharmacy Handling For IV
- IV flexibags should be stored and handled according to hospital infusion pharmacy SOPs.
- Avoid freezing intravenous products and follow local protocols for stock rotation.
- For online deliveries of IV or temperature‑sensitive products, use insulated packaging as required.
| Product | Storage Temperature |
|---|---|
| Tablets | 20–25°C (may be exposed 15–30°C) |
| IV Flexibags | Follow hospital protocols; avoid freezing |
Guidelines For Proper Use And Pharmacist Counselling Style (Australia)
Australian Pharmacist Counselling Approach
Prioritise patient safety through active screening and clear, practical counselling.
- Screen for absolute contraindications such as myasthenia gravis or prior quinolone tendon reactions.
- Review concomitant medicines that prolong QT, interact by chelation or increase tendon risk.
- Use teach‑back: ask the patient to repeat the dosing schedule and interaction warnings.
Patient Advice From PBS And National Health Authorities
- Tell patients to complete the course unless instructed otherwise by their prescriber.
- Advise separating antacids/minerals from avelox by 4–6 hours.
- Warn patients to report tendon pain, neuropathic symptoms or new CNS effects immediately.
- Discourage unnecessary antibiotic use for self‑limiting viral respiratory infections in line with stewardship advice.
- Counselling checklist: confirm indication, confirm understanding of dosing and interactions, provide written advice on red‑flag symptoms and reporting procedures to the TGA.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 9–14 days |
| Melbourne | Victoria | 9–14 days |
| Brisbane | Queensland | 9–14 days |
| Perth | Western Australia | 9–14 days |
| Adelaide | South Australia | 9–14 days |
| Canberra | Australian Capital Territory | 9–14 days |
| Hobart | Tasmania | 9–14 days |
| Darwin | Northern Territory | 9–14 days |
| Gold Coast | Queensland | 9–14 days |
| Newcastle | New South Wales | 9–14 days |
| Wollongong | New South Wales | 9–14 days |
| Townsville | Queensland | 14–21 days |
| Cairns | Queensland | 14–21 days |
| Launceston | Tasmania | 14–21 days |