Efexor
In brief
- In our pharmacy, you can buy efexor without a prescription, with delivery in 9–21 days throughout Australia. Discreet and anonymous packaging.
- Efexor (venlafaxine) is used to treat major depressive disorder, generalised anxiety disorder, social anxiety and panic disorder; it is a serotonin–noradrenaline reuptake inhibitor (SNRI) that increases levels of serotonin and noradrenaline in the brain.
- Usual dosage: immediate‑release commonly starts at 75 mg/day (divided) and XR at 75 mg once daily; maintenance typically 75–225 mg/day depending on the condition, with 225 mg/day a common maximum (IR doses up to 375 mg/day reported in some cases).
- Form of administration: oral tablets (immediate‑release) and extended‑release capsules/tablets taken by mouth.
- Onset time: some patients notice symptomatic improvement within 1–2 weeks, with full antidepressant effect generally seen by 4–6 weeks.
- Duration of action: extended‑release formulations provide once‑daily coverage (~24 hours); immediate‑release formulations have a shorter duration and are usually taken in divided doses (venlafaxine half‑life ~5 hours; active metabolite longer).
- Alcohol warning: avoid excessive alcohol—combining efexor with alcohol can increase sedation, impair coordination and worsen side effects or mood symptoms; avoid heavy drinking while taking this medicine.
- Most common side effect: nausea (other frequent effects include insomnia or drowsiness, dry mouth, sweating, sexual dysfunction and dose‑related increases in blood pressure).
- Would you like to try efexor without a prescription?
Safety, Warnings And Patient Protection (Australia)
Basic Efexor Information
- INN (International Nonproprietary Name): Venlafaxine
- Brand Names Available In Australia: Effexor; Effexor XR; Efexor (spelling variation used in the UK, Australia and New Zealand); plus generics such as Venlafaxine Sandoz, Teva and Mylan.
- ATC Code: N06AX16
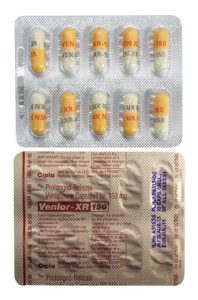
- Forms & Dosages: Immediate-release tablets — 25 mg, 37.5 mg, 50 mg, 75 mg, 100 mg; Extended-release capsules/tablets — 37.5 mg, 75 mg, 150 mg.
- Manufacturers In Australia: Originator and global suppliers include Pfizer; multiple generics from Teva, Sandoz, Mylan, Torrent and Aurobindo are commonly supplied to Australian pharmacies.
- Registration Status In Australia: Not specified in the provided product data; check the TGA Australian Register of Therapeutic Goods (ARTG) for current listings.
- OTC / Rx Classification: Prescription (Rx Only) in markets referenced in the product information.
Venlafaxine (INN: venlafaxine; brands include Effexor, Efexor and generics) is prescription-only in Australia and must be used under clinician and pharmacist supervision.
High-risk groups require particular monitoring and counselling when starting or changing venlafaxine therapy.
- Elderly patients: increased risk of hyponatraemia, falls and blood-pressure changes; check electrolytes and blood pressure at baseline.
- Pregnancy and breastfeeding: discuss potential risks and benefits with an obstetrician and the prescriber prior to starting or continuing treatment.
- Cardiovascular disease: venlafaxine may raise blood pressure in a dose-dependent way, so review cardiac history and monitor vitals.
- Seizure disorders and bipolar disorder: use caution and seek specialist input because venlafaxine can lower seizure threshold and may precipitate mania.
- Bleeding risk: review concomitant anticoagulant and antiplatelet therapy due to increased bleeding risk with serotonergic medicines.
- Absolute contraindication: concurrent monoamine oxidase inhibitor (MAOI) use or within 14 days of MAOI cessation.
Before dispensing, verify baseline blood pressure and review concomitant medications, with particular attention to anticoagulants and other serotonergic agents.
Document counselling and provide clear pharmacy contact details for any adverse-effect or withdrawal queries.
Monitoring Steps:
- Baseline blood pressure measurement prior to or at initiation of therapy.
- Electrolyte check (sodium) in elderly patients or those on diuretics.
- Medication review for serotonergic drugs, MAOIs, anticonvulsants and anticoagulants.
- Assess cardiovascular history and seizure risk before starting.
- Screen for current or past bipolar disorder and assess suicide risk at baseline and follow-up visits.
- Arrange follow-up contact with pharmacist or prescriber within 1–2 weeks of initiation or dose change.
Pregnancy/Breastfeeding Counselling Checklist:
- Confirm pregnancy status before starting venlafaxine where possible.
- Discuss known benefits of treating maternal depression versus potential neonatal adaptation effects.
- Advise collaboration with the obstetrician, paediatrician and prescriber for shared decision-making.
- Document informed discussion and plan for breastfeeding monitoring if continued during lactation.
High‑Risk Groups (Elderly, Pregnancy, Chronic Illness)
Elderly patients need the lowest effective dose and slow titration due to hyponatraemia and falls risk.
Pregnancy and breastfeeding require specialist discussion about risks and benefits rather than automatic discontinuation.
People with cardiovascular disease, a history of seizures, bipolar disorder or bleeding disorders require extra caution and monitoring.
Concurrent use of MAOIs is an absolute contraindication and must be avoided for at least 14 days after stopping an MAOI.
Q&A — “Can I Drive After Taking It In Australia?”
Q: Can I drive or operate machinery after taking venlafaxine?
A: Some people experience dizziness, drowsiness or blurred vision, especially during dose initiation or increase.
A: Australian workplace safety law expects you to be fit for duty, so do not drive or operate heavy machinery if you feel impaired.
A: Advise patients to test their reaction times in a safe environment before driving and report persistent impairment to the prescriber.
Usage Basics
INN, Brand Names Available In Australia
- INN: Venlafaxine.
- Common Brands: Effexor, Effexor XR and Efexor (spelling variation used regionally), plus generics from Teva, Sandoz and Mylan.
- Forms: Immediate-release tablets and extended-release (XR/MR) capsules/tablets.
When the prescription specifies XR or an equivalent brand such as Efexor XR 75mg, ensure the dispensing label and directions match the prescriber’s intent.
Legal Classification (TGA Approval, PBS)
Venlafaxine is a prescription medicine registered under ATC code N06AX16.
PBS subsidy status can vary by brand, indication and patient concession status, so always check the current PBS Schedule at pbs.gov.au.
- INN: Venlafaxine — ATC N06AX16.
- Common Brands: Effexor, Effexor XR, Efexor, generic venlafaxine products.
- Forms: Immediate-release and extended-release formulations in multiple strengths.
Pharmacists should verify authority prescriptions and record PBS item numbers on dispensing where applicable.
Dosing Guide
Standard Regimens (PBS Reference Dosing)
Typical adult dosing from product information should guide initial therapy and maintenance regimens.
For major depressive disorder, immediate-release is commonly started at 75 mg/day divided, or extended-release 75 mg once daily.
Maintenance doses for many indications range from 75 mg/day up to 225 mg/day, with some IR cases using up to 375 mg/day under close specialist supervision.
For generalised anxiety disorder and social anxiety disorder, extended-release 75 mg once daily is a common starting and maintenance dose, with titration up to 225 mg/day for GAD.
For panic disorder, start with XR 37.5 mg once daily and titrate to 75–225 mg/day as clinically required.
Adjustments For Comorbidities
Reduce the dose by approximately 50% for moderate to severe liver impairment and monitor closely.
In moderate to severe renal impairment, consider a reduction to 25–50% of the usual dosage and adjust to clinical response.
Elderly patients should receive the lowest effective dose with slow titration and frequent review of blood pressure and sodium.
Children and adolescents under 18 are not generally recommended to use venlafaxine due to limited data and suicidality concerns.
Q&A — “What If I Miss A Dose?”
Q: What should I do if I miss a dose?
A: Take the missed dose as soon as remembered unless the next dose is due soon, and do not double up to make up the missed dose.
A: For extended-release formulations, skip the missed dose and resume the usual schedule the next day.
A: If missed doses occur regularly or withdrawal symptoms start, contact the prescriber or pharmacist for advice.
Dosing Steps:
- Start at the prescriber’s recommended initial dose and schedule a follow-up within 1–2 weeks.
- Titrate slowly upward based on tolerance and clinical response.
- Monitor blood pressure periodically, especially at higher doses.
- Document all dose changes in the dispensing record and advise the patient to keep written directions.
| Regimen | Typical Starting Dose | Maintenance Dose |
|---|---|---|
| Major Depressive Disorder (Adults) | IR 75 mg/day (divided) or XR 75 mg once daily | Up to 225 mg/day (some IR cases up to 375 mg/day) |
| Generalised Anxiety Disorder | XR 75 mg once daily | 75–225 mg/day |
| Panic Disorder | XR 37.5 mg once daily | 75–225 mg/day |
Interaction Chart
Food And Drinks (Alcohol, Coffee, Australian Diet)
Alcohol can worsen depression, increase sedation and lower seizure threshold when combined with venlafaxine, so counsel avoidance or minimisation.
Caffeine may exacerbate anxiety and insomnia in some patients taking venlafaxine, so monitor caffeine intake.
Herbal products common in Australia such as St John’s wort can increase the risk of serotonin syndrome when taken with venlafaxine and should be avoided.
Common Drug Conflicts
High-risk interactions include monoamine oxidase inhibitors (MAOIs), which are contraindicated, and concurrent serotonergic medicines such as other SSRIs, SNRIs, tramadol and triptans.
Anticoagulants and antiplatelet agents raise bleeding risk when combined with venlafaxine, particularly in older adults.
Strong CYP inhibitors or inducers can alter venlafaxine plasma levels and require monitoring or dose adjustment.
| Drug Class | Effect | Clinical Action |
|---|---|---|
| MAOIs | Serotonin toxicity risk; contraindicated | Do not co-prescribe; allow 14-day washout after MAOI |
| Other Serotonergic Drugs (SSRIs, SNRIs, Triptans, Tramadol) | Increased serotonin syndrome risk | Monitor closely; consider alternative analgesia or taper strategies |
| Anticoagulants / NSAIDs | Increased bleeding risk | Monitor INR where relevant; counsel on bleeding signs |
| Strong CYP Inhibitors/Inducers | Altered venlafaxine levels | Adjust dose or monitor clinical effect and side effects |
User Reports & Trends (Australia)
What patients say: many report improved mood and reduced anxiety, often after SSRI failure, while others report tolerability issues early in treatment.
- Positive Trends: Improved energy, clearer thinking and quicker response in anxiety symptoms reported by some Australian patients.
- Adverse Trends: Common complaints include nausea, insomnia, sweating, sexual dysfunction and withdrawal symptoms on stopping.
- Rural and regional patients often note price sensitivity and a preference for generics to reduce out-of-pocket costs.
- Clinicians often choose venlafaxine when a noradrenergic effect is considered helpful in mixed anxiety-depressive presentations.
| Side Effect Frequency | Examples |
|---|---|
| Very Common | Nausea, vomiting |
| Common | Insomnia, drowsiness, dry mouth, sweating, sexual dysfunction |
| Occasional | Dizziness, nervousness, raised blood pressure |
Access & Purchase Options (Australia)
National Chains And Community Pharmacies
Venlafaxine is dispensed by major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, as well as independent community pharmacies.
Generics from suppliers like Teva, Sandoz and Mylan are commonly stocked and may offer cost savings for patients.
Online Pharmacies And Telehealth E‑Prescriptions
E-prescriptions issued by an AHPRA-registered prescriber via telehealth are acceptable at reputable Australian pharmacies.
In our online pharmacy, efexor is available without a prescription, with discreet delivery to Australia in 9-21 days.
Warn patients about overseas online sellers that do not require a valid prescription and advise using only Australian-registered services for safety and legal compliance.
Checklist: What A Pharmacy Needs:
- A valid prescription or electronic script from an AHPRA-registered prescriber.
- Patient identification where required for PBS subsidy verification and authority prescriptions.
- Confirmation of PBS concession or entitlement to apply relevant subsidies.
- Secure delivery address and instructions for temperature-sensitive handling where applicable.
Mechanism & Pharmacology
Simplified Explanation
Venlafaxine is a serotonin–noradrenaline reuptake inhibitor (SNRI) that increases synaptic serotonin and noradrenaline levels.
At lower doses the drug primarily inhibits serotonin reuptake, while at higher doses noradrenaline reuptake inhibition becomes more pronounced.
The dose-dependent noradrenergic effect helps explain differences in efficacy for certain symptoms and the increased risk of blood-pressure elevation at higher doses.
Extended-release formulations blunt peak plasma concentrations, which can improve tolerability and adherence compared with immediate-release dosing.
Clinical Terms
- SNRI: Serotonin–Noradrenaline Reuptake Inhibitor.
- INN: International Nonproprietary Name — venlafaxine.
- XR/MR: Extended-Release / Modified-Release formulations.
- ATC Code: N06AX16.
Indications & Off‑Label Uses
Approved Indications By TGA
Based on product information and registration in other comparable jurisdictions, venlafaxine is indicated for major depressive disorder, generalised anxiety disorder, social anxiety disorder and panic disorder.
Confirm exact TGA Product Information and ARTG entries for proprietary brands sold in Australia prior to prescribing or dispensing.
Off‑Label Uses In Australian Practice
- Off‑label use may include certain chronic pain syndromes and menopausal vasomotor symptoms in select cases under specialist oversight.
- Off‑label prescribing should involve documented rationale, informed consent and a monitoring plan for adverse effects.
Checklist For Off‑Label Prescribing:
- Document the clinical rationale and evidence summary in the patient record.
- Obtain and note informed consent from the patient that explains uncertainty of benefit and potential risks.
- Arrange defined monitoring milestones and follow-up to assess efficacy and tolerability.
Key Clinical Findings (2022–2026)
Recent systematic reviews and meta-analyses to 2026 continue to support venlafaxine’s efficacy in major depressive disorder and several anxiety disorders.
Some evidence suggests venlafaxine can produce faster symptom reduction versus certain SSRIs, but it is associated with higher rates of nausea, blood-pressure elevation and withdrawal symptoms.
Comparative effectiveness versus duloxetine and desvenlafaxine varies by patient population and comorbidities, so individualised choice is recommended.
- Benefits: Effective for MDD and anxiety disorders, useful when SSRI response was inadequate.
- Risks: Higher incidence of nausea, dose-dependent BP rise and notable discontinuation symptoms.
| Outcome Domain | Evidence Strength |
|---|---|
| Efficacy For MDD/Anxiety | Moderate to Strong |
| Tolerability (GI, Sweating, Sexual) | Moderate |
| Cardiovascular Risk (BP Elevation) | Moderate; dose-dependent |
Alternatives Matrix
PBS‑Listed Alternatives Comparison Table
| Drug | Mechanism | Typical PBS Dosing | Common Side Effects | Clinical Scenarios Favouring Choice |
|---|---|---|---|---|
| Sertraline | SSRI | Typically 50–200 mg daily | Nausea, insomnia, sexual dysfunction | Often preferred in pregnancy planning and initial SSRI trials |
| Escitalopram | SSRI | Typically 10–20 mg daily | Headache, nausea, sexual dysfunction | Well tolerated in some with fewer drug interactions |
| Duloxetine | SNRI | Usually 30–60 mg daily | Nausea, dry mouth, sweating | Favoured when neuropathic pain co-exists with depression |
| Desvenlafaxine | SNRI | Typically 50 mg daily | Nausea, insomnia, dizziness | Consider when venlafaxine is not tolerated or when metabolic pathways differ |
Pros And Cons Checklist
- Review prior SSRI response before choosing venlafaxine or an alternative.
- Consider side-effect profiles: venlafaxine has stronger noradrenergic effects at higher doses.
- Assess blood pressure and bleeding risk when weighing options.
- Factor in cost and PBS availability, including brand and concession eligibility.
- Consider interactions with existing medicines and comorbid conditions.
Common Questions (Pharmacy Consultations)
How long until it works?
Most patients notice some improvement in 2–6 weeks, with up to 12 weeks for full effect.
Are sexual side effects common?
Sexual dysfunction is a common adverse effect and worth discussing before treatment; alternative strategies include dose adjustment or switching agents.
How to switch from an SSRI?
Switching requires planning around washout periods and monitoring for serotonin syndrome; consult the prescriber for a supervised switch.
What about pregnancy and breastfeeding?
Discuss risks of medication exposure versus relapse risk with the prescriber and obstetric team to make an individualised plan.
How to avoid withdrawal?
Taper slowly under clinical supervision to reduce discontinuation symptoms rather than stopping abruptly.
Micro‑FAQ: If nausea starts when beginning treatment, try taking the dose with food and report persistent symptoms to the pharmacist.
Encourage patients to contact the pharmacist or prescriber if issues are unresolved or if suicidal ideation emerges.
Price & Access Comparison Table
Comparison Table — Pharmacy/Source, Typical Price Range, PBS Subsidy Status, Prescription Required
| Source | Typical Price Range | PBS Subsidy | Prescription Required |
|---|---|---|---|
| Community Pharmacies (In‑Store) | Varies by brand and concession | Yes, check PBS item numbers and eligibility | Yes |
| Major Chains (Chemist Warehouse, Priceline) | Varies; generics often cheaper | Yes, subject to PBS rules | Yes |
| Online Australian Pharmacies | Varies; may offer discreet delivery | May apply if PBS-eligible and prescription provided | Yes |
| International Suppliers | Varies; caution advised | No — verify local subsidy | Often no valid prescription required by seller — avoid |
Access Checklist — Major Chains, Online Pharmacies, Rural Vs Urban Availability
- Confirm the prescription is valid and from an AHPRA-registered prescriber.
- Check PBS eligibility and any authority requirements prior to dispensing.
- Ask about delivery time and packaging, especially for rural addresses and hot weather transit.
- Advise patients to check real-time retail prices at their chosen pharmacy as prices vary.
Registration & Regulation
TGA Approval
Venlafaxine is listed under ATC N06AX16 and is a prescription medicine registered with regulatory authorities in multiple jurisdictions.
For specific Australian brand registrations and Product Information, consult the TGA ARTG database.
PBS Subsidy Details
PBS listings, subsidy status and restrictions can change, so pharmacists must verify current PBS Schedule entries before dispensing.
Brand substitution and generic supplies are common; record the dispensed brand on the patient’s record for traceability.
Regulatory Checks Checklist:
- Confirm the ARTG number for the specific product being dispensed when necessary.
- Verify PBS item number and authority requirements on government resources.
- Document the dispensed brand and batch where required for pharmacovigilance.
Storage & Handling
Household Storage In Australian Climate (Heat/Humidity)
Store venlafaxine at 20–25°C in its original packaging and away from moisture and heat.
Avoid storing medicines in bathrooms or cars where temperature and humidity fluctuate, especially in Australian summers.
Keep all medicines out of reach of children and pets.
Cold‑Chain Handling For Pharmacies
Venlafaxine does not require refrigeration, but pharmacies should avoid extremes of temperature in dispensary storage.
For mail order and delivery, use sealed packaging and expedite transit to avoid prolonged exposure to high temperatures.
Storage Tips:
- Advise patients to store tablets in a cool, dry cupboard away from direct sunlight.
- For hot regions, suggest storing medications in an internal cupboard rather than near windows.
- Instruct patients to check tablets for unusual odour, discolouration or crumbling if exposed to extreme heat, and to contact the pharmacy if concerned.
If Tablets Are Exposed To Extreme Heat:
- Do not use if the product shows obvious degradation.
- Contact the dispensing pharmacy for advice and possible replacement.
- Record and report any suspected product quality issue to the supplier and the TGA if appropriate.
Guidelines For Proper Use (Pharmacist Counselling)
Australian Pharmacist Counselling Style
Confirm the indication, intended duration and whether the prescriber specified XR or immediate-release formulation at the time of dispensing.
Explain the starting dose, titration plan and when to expect symptom changes.
Discuss the most common side effects including nausea, sweating, sexual dysfunction, insomnia and the possibility of raised blood pressure at higher doses.
Review interactions with MAOIs, anticoagulants, OTC analgesics, herbal remedies and other serotonergic medicines.
Provide clear instructions on missed doses and advise patients not to stop abruptly because withdrawal symptoms can occur.
Document counselling in the patient’s pharmacy record and arrange for follow-up contact.
Patient Advice From PBS And National Health Authorities
Encourage patients to record medicines on My Health Record and to keep the Consumer Medicine Information leaflet for reference.
Direct patients to the TGA and PBS websites for authoritative product and subsidy information and advise them to confirm PBS eligibility before filling scripts.
For suicidal ideation or severe adverse effects, instruct immediate contact with the prescriber or local emergency services.
- Provide written medicine information and check patient understanding before they leave the pharmacy.
- Advise on scheduling BP checks if taking higher doses or if there is a history of hypertension.
- Keep a documented follow-up plan and pharmacy contact details visible on the dispensing record.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9-14 days |
| Melbourne | Victoria | 9-14 days |
| Brisbane | Queensland | 9-14 days |
| Perth | Western Australia | 9-14 days |
| Adelaide | South Australia | 9-14 days |
| Canberra | Australian Capital Territory | 9-14 days |
| Gold Coast | Queensland | 9-14 days |
| Newcastle | New South Wales | 9-14 days |
| Wollongong | New South Wales | 9-14 days |
| Sunshine Coast | Queensland | 9-14 days |
| Geelong | Victoria | 9-14 days |
| Hobart | Tasmania | 14-21 days |
| Darwin | Northern Territory | 14-21 days |
| Townsville | Queensland | 14-21 days |
| Cairns | Queensland | 14-21 days |