Lozol
In brief
- You can obtain Lozol from pharmacies (marketed as Lozol and other indapamide brands); officially it is prescription-only (Rx) in most countries, although availability without a prescription may occur in some pharmacies or online suppliers depending on local regulations.
- Lozol (indapamide) is used to treat hypertension and oedema (including congestive heart failure); it is a thiazide‑like diuretic that reduces sodium reabsorption in the distal renal tubule, causing natriuresis and diuresis, lowering blood volume and blood pressure, and it also has some vasodilatory effects on blood vessels.
- Usual adult doses are 1.25 mg or 2.5 mg once daily for hypertension; 2.5 mg once daily is commonly used for oedema/heart failure; elderly patients are usually started on the lower 1.25 mg dose.
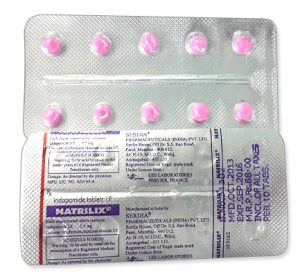
- Lozol is given orally as tablets (commonly 1.25 mg and 2.5 mg).
- Diuretic effects usually begin within 1–2 hours; measurable blood-pressure reduction often starts within 24–48 hours, with full antihypertensive benefit developing over 2–4 weeks.
- The duration of action supports once-daily dosing (effects generally last about 24 hours, with sustained blood-pressure benefit when taken daily).
- Avoid or limit alcohol while taking Lozol — alcohol can worsen dizziness and low blood pressure and increase the risk of fainting and dehydration.
- The most common side effect is an electrolyte disturbance, particularly low potassium (hypokalaemia); dizziness, headache and fatigue are also commonly reported.
- Would you like to try lozol without a prescription?
Critical Warnings & Restrictions (Safety First)
Basic Lozol Information
- INN (International Nonproprietary Name): Indapamide.
- Brand Names Available In Australia: not specified.
- ATC Code: C03BA11.
- Forms & Dosages: Tablets 1.25 mg, 2.5 mg; no other forms specified.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription only (Rx) worldwide.
Before any clinical detail, safety must be clear.
Indapamide is prescription-only worldwide and can cause significant changes in electrolytes and fluid volume.
Australian patients must consult a prescriber or pharmacist before starting indapamide.
High-Risk Groups (Elderly, Pregnancy, Chronic Illness)
Do not prescribe or supply indapamide without assessing contraindications and baseline labs.
Absolute contraindications include known allergy to indapamide or sulfonamides, severe renal failure (anuria or eGFR <30 mL/min), severe hepatic impairment or hepatic encephalopathy, existing hypokalaemia or severe hyponatraemia, and pregnancy or breastfeeding unless a specialist advises otherwise.
Elderly patients require the lowest effective starting dose, typically 1.25 mg once daily, and closer monitoring for dehydration, falls risk and hypokalaemia.
Patients with diabetes, gout or those taking multiple antihypertensives need more frequent review and laboratory checks for electrolytes and renal function.
Use the following checklist in clinic before initiating indapamide.
- Allergies to indapamide or sulfonamides confirmed.
- Current medications including over-the-counter NSAIDs, lithium, corticosteroids and supplements recorded.
- Baseline eGFR and serum electrolytes (sodium, potassium, magnesium) available.
- Pregnancy test performed if childbearing potential and contraception status discussed.
- Recent falls or orthostatic symptoms queried and documented.
- Blood pressure both supine and standing if fall risk suspected.
Interaction With Activities (Driving, Workplace Safety Under Australian Law)
Dizziness and light-headedness are known side effects when starting or changing the dose of indapamide.
Counsel patients to avoid driving or operating heavy machinery until they know how the medicine affects them.
- Do not drive if feeling dizzy, faint or having blurred vision after a dose change.
- Avoid high-risk work at the start of treatment or after dose adjustments until tolerated.
- Advise hydration and slow position changes to reduce orthostatic symptoms.
- Discuss workplace safety with employers where required under local policies for medical fitness to perform safety-critical tasks.
Q&A — “Can I Drive After Taking It In Australia?”
Q: Can I drive after taking indapamide?
A: If you feel dizzy, light-headed or have blurred vision after starting or changing dose, do not drive or operate machinery.
A: Report new symptoms to your prescriber and follow AustRoads guidance on fitness to drive for medical conditions and medications.
Usage Basics
INN, Brand Names Available In Australia
Patients commonly search for lozol and indapamide tablets when researching options for high blood pressure.
International brand names include Lozol (Sanofi Aventis US), Natrilix and Fludex (Servier), plus many generics from companies such as Cipla and KRKA.
In Australia, brand availability varies and should be checked against TGA listings and major pharmacy suppliers.
- Lozol — Sanofi Aventis (international).
- Natrilix / Fludex — Servier (international).
- Indapamide generics — multiple manufacturers internationally (Cipla, KRKA, others).
| Product/Brand | TGA Registration (Y/N) | PBS Listed (Y/N) | Typical Pack/Dose |
|---|---|---|---|
| Lozol (Sanofi) | not specified | not specified | Tablets 1.25 mg, 2.5 mg |
| Natrilix / Fludex (Servier) | not specified | not specified | Tablets 2.5 mg or blister |
| Indapamide Generics | not specified | not specified | Tablets 1.25 mg, 2.5 mg |
Legal Classification (TGA-Approved, PBS-Listed)
Indapamide is prescription-only worldwide according to available product information.
Australian clinicians must verify current TGA registration and PBS listing for subsidy eligibility before prescribing.
Telehealth e-prescriptions are accepted for chronic supply, and rural patients may need postal delivery or a local chemist to check stock.
| Product/Brand | TGA Registration (Y/N) | PBS Listed (Y/N) | Typical Pack/Dose |
|---|---|---|---|
| Lozol | not specified | not specified | 1.25 mg, 2.5 mg |
| Generics | not specified | not specified | 1.25 mg, 2.5 mg |
Dosing Guide
Standard Regimens (PBS Reference Dosing)
Standard adult doses are 1.25 mg or 2.5 mg once daily for hypertension and 2.5 mg once daily for oedema or congestive heart failure.
Start elderly patients at the lowest dose, typically 1.25 mg daily, and titrate according to response and laboratory results.
Indapamide is usually taken in the morning to reduce nocturia and minimise falls risk.
Adjustments For Comorbidities
Indapamide is not recommended for children due to insufficient data.
It is contraindicated in severe renal impairment (eGFR <30 mL/min) and should be used cautiously in mild-to-moderate renal or hepatic impairment with frequent monitoring.
When combined with other diuretics, ACE inhibitors, ARBs or potassium-depleting agents, adjust dosing and monitor electrolytes closely.
Q&A — “What If I Miss A Dose?”
Q: What should I do if I miss a dose of indapamide?
A: Take it as soon as you remember.
A: If it is near the time of your next dose, skip the missed dose and resume your regular schedule; do not double up.
A: Contact your pharmacist if you miss doses regularly or are unsure about dosing.
Use the following checklist for titration and monitoring.
- Baseline labs: eGFR, electrolytes (Na, K, Mg), uric acid if gout history.
- Early review: 1–2 weeks after initiation or dose change for electrolytes and renal function.
- Follow-up: 3 months for clinical response and adherence checks.
- Ongoing: periodic monitoring every 6–12 months or sooner if clinically indicated.
Interaction Chart
Food And Drinks (Alcohol, Coffee, Australian Diet Context)
Alcohol can increase dizziness and orthostatic hypotension risk while adjusting to indapamide.
High-sodium diets blunt antihypertensive response, so counsel Australian patients about common salty foods such as processed pies, takeaway meals and packaged snacks.
Caffeine may temporarily blunt diuresis but has minimal clinically significant interaction with indapamide.
Common Drug Conflicts
Key drug interactions include additive blood-pressure lowering with other antihypertensives and effects on potassium handling that can alter cardiac risk.
| Interacting Drug | Effect | Monitoring Advice |
|---|---|---|
| ACE Inhibitors / ARBs | Added hypotension; potential hyperkalaemia shifts or hypokalaemia depending on combination | Monitor BP and electrolytes within 1–2 weeks of combination. |
| Other Diuretics (Thiazide/Loop) | Increased risk of volume depletion and electrolyte imbalance | Check renal function and electrolytes; consider dose reduction. |
| Lithium | Risk of lithium toxicity due to altered renal handling | Avoid combination if possible; monitor lithium levels closely if co-prescribed. |
| NSAIDs | May reduce antihypertensive efficacy and increase renal risk | Advise patients to avoid regular NSAID use and monitor renal function. |
| Corticosteroids / Laxatives | Increased risk of hypokalaemia | Monitor potassium and adjust therapy as required. |
| Drugs That Prolong QT / Potassium-Wasting Agents | Combined hypokalaemia raises arrhythmia risk | Monitor electrolytes and ECG if severe electrolyte disturbance suspected. |
Remember to check for combination products sold internationally, such as indapamide with perindopril or amlodipine, when reconciling medicines.
User Reports & Trends
Patients often report that low doses of indapamide effectively reduce blood pressure with a tolerable side-effect profile.
Common patient complaints include dizziness, muscle cramps and laboratory-detected electrolyte changes.
Cost sensitivity and a preference for generics are frequent themes in Australian patient feedback.
- Side effects: dizziness, cramps, fatigue.
- Monitoring concerns: frequency of blood tests for electrolytes and renal function.
- Pill size and timing: morning dosing preferred to avoid nocturia.
- Postal delivery: rural patients often request mail-order supply for convenience.
| Sentiment | Likely Clinical Action |
|---|---|
| Positive | Continue at current dose and monitor routinely. |
| Neutral | Review adherence, counsel on diet and timing, check labs. |
| Negative | Adjust dose, consider alternative diuretic or add potassium monitoring. |
In Australia there is strong reliance on PBS subsidies and pharmacist advice when choosing brands and switching suppliers.
- Efficacy
- Measured reduction in blood pressure and clinical outcomes as reported by patients and trials.
- Tolerability
- Patient-reported side effects such as dizziness, cramps and electrolyte issues.
- Adherence
- Ease of once-daily dosing, cost and supply stability affecting ongoing use.
Access & Purchase Options
National Chains (Chemist Warehouse, Priceline, TerryWhite)
Indapamide is prescription-only and major chains can advise on substitutions and stock availability.
Bring a current medication list, recent pathology results and your PBS concession card if eligible when collecting a repeat supply.
- Bring current medication list and recent pathology to the pharmacy.
- Carry PBS concession card if eligible to reduce cost.
- Bring photo ID if requesting a new supply or repeat pickup through the pharmacy.
Online Pharmacies And Telehealth E-Prescriptions
Telehealth e-prescriptions are widely used and are valid at both online and brick-and-mortar pharmacies in Australia.
For rural or remote patients, pharmacies can post medicines; indapamide does not require cold-chain handling and should be stored below 25°C.
In our online pharmacy, lozol is available without a prescription, with discreet delivery to Australia in 9-21 days.
| Local Pharmacy | Online Pharmacy | Telehealth Script | Typical Wait And Cost |
|---|---|---|---|
| Brick-and-mortar chain | Australian online pharmacy | Accepted at most pharmacies | Same day to 3 days; cost varies by brand and PBS status |
| Independent pharmacy | Mail-order options | Accepted; check dispensing pharmacy | 1–7 days; rural posting 9–21 days; cost varies |
Only use TGA-approved Australian online pharmacies and confirm that a valid prescription is required before purchase.
Mechanism & Pharmacology
Simplified Explanation
Indapamide is a thiazide-like diuretic with ATC code C03BA11 that lowers blood pressure by increasing sodium and water excretion.
Its diuretic action reduces circulating volume acutely, and vascular effects reduce peripheral resistance over time.
Clinical Terms
Onset of diuresis occurs within hours, and once-daily dosing provides sustained antihypertensive effect.
Typical tablet strengths sold internationally are 1.25 mg and 2.5 mg, and no injectable or topical forms are available.
- Formulation: oral tablets, 1.25 mg and 2.5 mg.
- Dosing frequency: once daily.
- Typical onset: diuretic effect within hours; antihypertensive effect sustained with chronic dosing.
- Elimination: adjust use in renal impairment and monitor electrolytes.
Clinicians should monitor electrolytes and renal function, and be alert for signs of hypokalaemia and hyponatraemia such as muscle cramps, arrhythmias and confusion.
- Natriuresis
- Increased renal sodium excretion leading to reduced fluid volume.
- Hypokalaemia
- Low serum potassium that can cause weakness, cramps and ECG changes.
- eGFR
- Estimated glomerular filtration rate, a key measure of renal function used to guide use.
Indications & Off-Label Uses
Approved Indications By TGA
Internationally indapamide is indicated for hypertension and for oedema or congestive heart failure.
Recommended doses include 1.25–2.5 mg once daily for hypertension and 2.5 mg once daily for oedema/CHF.
Clinicians in Australia should confirm TGA-approved indications and local product information before prescribing.
Off-Label Uses In Australian Clinical Practice
Off-label roles include using indapamide as part of combination therapy for resistant hypertension and for vascular-protection strategies in older patients.
- Consider off-label use only with clinical justification and documented informed consent.
- Monitor electrolytes and renal function more frequently in off-label scenarios.
- Discuss reproductive risks with women of childbearing potential before off-label prescribing.
Key Clinical Findings
Recent international studies show indapamide provides sustained blood-pressure reduction and, when combined with ACE inhibitors, may reduce stroke risk in some trials.
Outcomes in elderly patients are favourable compared with classic thiazides for vascular health, though electrolyte disturbances and raised uric acid are consistent safety signals.
| Study/Year | Population | Key Outcome | Safety Signals |
|---|---|---|---|
| International Trials (Recent) | Adults with hypertension | Sustained BP reduction; reduced stroke risk when combined with ACE inhibitor | Hypokalaemia, hyponatraemia, increased uric acid |
| Elderly Patient Studies | Older hypertensive adults | Favourable vascular outcomes vs classic thiazides | Electrolyte disturbances noted |
- Monitor electrolytes early and periodically after initiation or dose change.
- Consider baseline ECG when severe hypokalaemia risk exists.
- Weigh alternatives if repeated intolerance or symptomatic electrolyte imbalance occurs.
Always consult up-to-date RACGP guidance, Cardiac Society statements and local TGA product information before applying trial data to practice.
Alternatives Matrix
PBS-Listed Alternatives Comparison Table
| Drug (INN) | Typical Dose | Mechanism | Pros | Cons | PBS Status |
|---|---|---|---|---|---|
| Hydrochlorothiazide | 12.5–50 mg daily | Thiazide diuretic | Commonly used, low cost | Shorter half-life; metabolic effects | varies by formulation |
| Chlorthalidone | 12.5–25 mg daily | Thiazide-like, longer-acting | Longer-acting, potent natriuresis | Potential for greater hypokalaemia | varies by formulation |
| Furosemide | 20–80 mg daily (variable) | Loop diuretic | Powerful diuresis for volume overload | Not first-line for hypertension; shorter duration | varies by formulation |
Pros And Cons Checklist
- Consider efficacy for BP control versus risk of hypokalaemia.
- Assess comorbidities such as gout, diabetes and renal disease when choosing therapy.
- Factor in cost and PBS subsidy when advising patients on long-term use.
- Choose once-daily agents to support adherence where possible.
Indapamide is often preferred in older patients for its vascular profile and as part of combination therapy when monotherapy is insufficient.
Common Questions (Pharmacy Counselling)
Patients commonly ask whether indapamide will cause frequent urination, whether blood tests are needed and if it interacts with other blood-pressure medicines.
- Will indapamide make me urinate a lot? Usually milder at low doses; take in the morning to limit nocturia.
- Do I need blood tests? Yes; baseline electrolytes and renal function, then early review at 1–2 weeks and periodic checks.
- Can I take other BP meds? Often yes, but interactions and additive effects require monitoring.
- Is it on the PBS? Check current PBS listings for item numbers and subsidy details before advising cost expectations.
Use this brief script when counselling patients.
- Confirm full name, indication and that baseline tests have been done.
- Explain dosing: once daily in the morning and what to do for missed doses.
- Review concurrent medicines, especially lithium, NSAIDs and potassium supplements.
- Advise on signs of hypokalaemia and hyponatraemia and when to seek urgent care.
Document counselling in the shared health record and inform the patient’s GP when treatment is started or interrupted.
Price & Access Comparison Table
Comparison Table — Pharmacy/Source, Typical Price Range, PBS Subsidy Status, Prescription Required
| Source | Typical Cost (Generic Range) | PBS Subsidy | Prescription Required | Delivery Options |
|---|---|---|---|---|
| Major Chain (Chemist Warehouse) | Varies by brand; check pharmacy | Check PBS item | Yes | In-store, local delivery, mail-order |
| Independent Pharmacy | Varies | Check PBS item | Yes | In-store, local delivery |
| Online Australian Pharmacy | Varies; may include postage | Check PBS item | Yes | Postal delivery (9–21 days for remote areas) |
| Hospital Discharge Supply | Often subsidised | Typically covered in discharge planning | Yes | Collect from hospital pharmacy |
Access Checklist — Major Chains, Online Pharmacies, Rural Vs Urban Availability
- Check PBS eligibility before prescribing or dispensing.
- Request repeats via telehealth where available to reduce travel for chronic patients.
- Consider mail-order for rural patients and confirm estimated delivery times.
- Ask the pharmacist about generic substitution and advise patients to stick with the same brand where possible for consistency.
- Pharmacies can provide blister packs and dose reminders to support adherence.
Registration & Regulation
TGA Approval
Verify TGA registration for the specific indapamide product and formulation before prescribing or dispensing in Australia.
Global approvals exist (FDA, EMA and other national agencies) but local TGA product information governs labelling and approved indications in Australia.
PBS Subsidy Details
Check the PBS schedule for item numbers, authority requirements and patient co-payment or concession rules.
If a product is not PBS-listed, patients will pay full price and clinicians should document clinical justification for non-PBS prescribing.
| Regulatory Body | Info To Verify | Where To Check |
|---|---|---|
| TGA | Registration, approved indications, product information | TGA website |
| PBS | Subsidy status, item numbers, authority rules | PBS schedule website |
Storage & Handling
Household Storage In Australian Climate (Heat/Humidity)
Store indapamide below 25°C, protected from light and moisture.
Advise patients in hot and humid regions to keep tablets in their original container and avoid storing them in the bathroom or near a stove.
Do not refrigerate or freeze the tablets and keep them out of reach of children.
For remote patients, insulated mailers are not required but protect the medicine from prolonged exposure to heat.
Cold-Chain Handling For Pharmacies
Indapamide is not a cold-chain product and standard ambient storage suffices.
- Check expiry dates and integrity of blister packs or bottles before dispensing.
- Maintain records of storage conditions and rotate stock to prevent heat exposure.
- In disaster situations such as floods or heatwaves, advise patients to move medicines to a cool place and contact the pharmacy for replacements if stock was compromised.
Guidelines For Proper Use
Australian Pharmacist Counselling Style
Begin counselling by confirming the patient’s name and the indication — hypertension or oedema.
Verify that baseline tests are completed and review current medicines, including complementary and OTC products.
Explain dosing clearly: once daily in the morning and what to do if a dose is missed.
Advise on side effects to report immediately, including severe weakness, fainting, irregular heartbeat or severe GI symptoms.
- Confirm pregnancy or breastfeeding status before supply.
- Arrange follow-up labs in 1–2 weeks after initiation or dose change.
- Record counselling in the patient’s record or My Health Record.
Patient Advice From PBS And National Health Authorities
Encourage patients to read Consumer Medicines Information when available and to follow GP and laboratory monitoring schedules.
Emphasise adherence and repeat-prescription processes and remind patients not to double up on missed doses.
- When To Seek Urgent Care: severe weakness, fainting, chest pain, palpitations or sudden severe confusion.
- Hypokalaemia Signs: muscle cramps, weakness, irregular heartbeat.
- Hyponatraemia Signs: confusion, severe lethargy, seizures in extreme cases.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9-14 days |
| Melbourne | Victoria | 9-14 days |
| Brisbane | Queensland | 9-14 days |
| Perth | Western Australia | 9-14 days |
| Adelaide | South Australia | 9-14 days |
| Canberra | Australian Capital Territory | 9-14 days |
| Hobart | Tasmania | 9-14 days |
| Darwin | Northern Territory | 9-14 days |
| Gold Coast | Queensland | 9-14 days |
| Newcastle | New South Wales | 9-14 days |
| Wollongong | New South Wales | 9-14 days |
| Geelong | Victoria | 9-14 days |
| Cairns | Queensland | 14-21 days |
| Townsville | Queensland | 14-21 days |
Final Notes And Clinician Reminders
Indapamide is a useful thiazide-like diuretic for hypertension and oedema when used with appropriate monitoring.
Always verify contraindications such as severe renal or hepatic impairment and pregnancy before starting therapy.
Monitor electrolytes and renal function at baseline, 1–2 weeks after starting, and periodically thereafter.
Discuss cost and supply options with patients and confirm PBS status prior to prescribing if subsidy is required.
When in doubt about interactions or patient suitability, consult local TGA product information or specialist guidance.