Minirin
In brief
- In our pharmacy, you can buy minirin without a prescription, with delivery in 9–21 days throughout Australia. Discreet and anonymous packaging.
- Minirin (desmopressin acetate) is used as an antidiuretic hormone replacement and a haemostatic agent — commonly for central diabetes insipidus, primary nocturnal enuresis and certain bleeding disorders (mild haemophilia A, type 1 von Willebrand disease). It acts on renal V2 receptors to increase water reabsorption and raises plasma factor VIII and von Willebrand factor to reduce urine output and improve haemostasis.
- Usual doses vary by indication and formulation: oral/ODT ranges around 60–240 µg (0.06–0.24 mg) for nocturnal enuresis, oral maintenance dosing commonly 0.05–0.4 mg daily divided for diabetes insipidus; nasal dosing often 10 µg per spray (individual titration required); injectable doses are much smaller and used in specialised settings — dosing must be guided by a clinician or product instructions.
- Forms of administration include tablets, orally disintegrating tablets (Melt), intranasal spray or drop (metered pump or rhinal tube), and injection (IV/SC/IM) in hospital settings.
- Onset of effect depends on route: IV/IM can act almost immediately, nasal typically within 15–30 minutes, and oral/ODT usually within 30–60 minutes.
- Duration of action varies with formulation and dose — typically from about 6 to 24 hours; many patients experience an 8–12 hour antidiuretic effect after a single dose.
- Do not consume alcohol — alcohol increases the risk of fluid imbalance and hyponatraemia while taking desmopressin.
- The most common side effect is headache; other important effects include nausea, facial flushing and the risk of hyponatraemia (low blood sodium), especially with excessive fluid intake.
- Would you like to try minirin without a prescription?
Critical Warnings & Restrictions — Safety First (Australian Patients)
Basic Minirin Information
- INN (International Nonproprietary Name): Desmopressin Acetate.
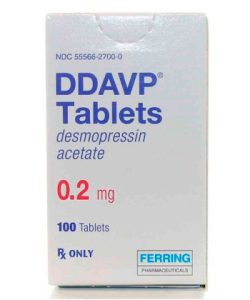
- Brand Names Available In Australia: DDAVP; regional brands include Minirin and other desmopressin generics (availability varies by product and supplier).
- ATC Code: H01BA02 — Desmopressin.
- Forms & Dosages: Not specified for all Australian pack sizes in the source data; commonly reported forms internationally include tablets (0.1 mg, 0.2 mg), orally disintegrating tablets/ODT (60 µg, 120 µg, 240 µg), nasal spray (10 µg per spray) and injection/ampoules for parenteral use.
- Manufacturers In Australia: Not specified in the source data.
- Registration Status In Australia: Not specified in the source data; clinicians should confirm specific product registration in the ARTG.
- OTC / Rx Classification: Not specified in the source data for Australia; check TGA and product information.
High-Risk Groups (Elderly, Pregnancy, Chronic Illness)
Who worries about this medicine most? Elderly patients, infants, pregnant or breastfeeding women and people with chronic disease are at the top of the list.
Desmopressin acetate can cause hyponatraemia due to water retention.
Patients with impaired renal function are at higher risk of water intoxication and symptomatic hyponatraemia.
People with heart failure should be closely monitored because fluid retention can worsen symptoms.
Patients with the syndrome of inappropriate antidiuretic hormone secretion (SIADH) are at particular risk of severe hyponatraemia on desmopressin.
The elderly are more susceptible to water imbalance and to the cognitive effects of low sodium.
Infants and young children can develop water intoxication more quickly than older children or adults.
Pregnancy and breastfeeding: use only if clearly needed and under specialist advice.
Discuss the risk–benefit with the obstetric team before starting desmopressin in pregnancy.
Chronic illness review: assess comorbidities such as chronic kidney disease, cirrhosis and uncontrolled hypertension before starting desmopressin.
Checklist Before Starting Desmopressin:
- Baseline sodium: Check serum sodium before initiation.
- Renal function: Review eGFR and recent renal tests.
- Fluid advice: Provide clear instructions on fluid restriction, especially overnight for nocturnal use.
- Monitoring schedule: Plan sodium checks after initiation and after dose changes, and arrange ongoing monitoring for high‑risk patients.
Interaction With Activities (Driving, Workplace Safety Under Australian Law)
Severe hyponatraemia can present with drowsiness, dizziness or seizures and may impair driving or operating machinery.
Patients must be advised to avoid driving or operating heavy machinery until symptoms have resolved and their treating clinician confirms stability.
Employers, especially in safety‑sensitive industries, should be informed where legally required and where safety may be affected.
Q&A — “Can I Drive After Taking It In Australia?”
Short answer: not if you experience dizziness, drowsiness, headaches or visual disturbance.
If you feel well and have no symptoms then follow usual driving laws and clinician advice.
Report any adverse effects to your prescriber or pharmacist and do not drive until symptoms resolve.
- Do not drive if you have dizziness.
- Do not drive if you feel drowsy or confused.
- Do not drive if you have new headaches or visual disturbance.
- Seek urgent care for seizures, severe confusion or collapse.
Usage Basics — Identity, Brands And Legal Status
INN, Brand Names Available In Australia
The International Nonproprietary Name is desmopressin acetate.
Key brands globally include DDAVP and Minirin, with various generics available in many markets.
Common formulations reported internationally are tablets, orally disintegrating tablets (ODT), nasal sprays and injection.
- ODT strengths commonly reported: 60 µg, 120 µg, 240 µg.
- Tablet strengths commonly reported: 0.1 mg and 0.2 mg.
- Nasal spray: ~10 µg per spray (0.01% solution) as commonly described in international packaging examples.
Legal Classification (TGA-Approved, PBS-Listed)
Desmopressin is generally a prescription-only medicine in most jurisdictions; confirm TGA status for specific products in Australia.
PBS listing and subsidy depend on formulation and approved indication and can change over time.
- TGA
- The Therapeutic Goods Administration is the regulator that approves medicines and registers products on the ARTG.
- PBS
- The Pharmaceutical Benefits Scheme may subsidise specific formulations for listed indications; check the current PBS schedule for criteria and item numbers.
- Pharmacist Supply
- Pharmacists should verify prescription status, check authority requirements for PBS items and provide counselling at dispensing.
Dosing Guide — Practical Regimens And Adjustments
Standard Regimens (PBS Reference Dosing)
Dosing of desmopressin varies by indication and formulation and is usually individually titrated for central diabetes insipidus.
For primary nocturnal enuresis, fixed night‑time doses of ODT or tablets are commonly used under prescriber guidance.
- Typical product strengths and routes include tablets (0.1 mg, 0.2 mg), ODT (60–240 µg), nasal solutions (~10 µg per spray) and parenteral ampoules for IV/SC/IM use.
Adjustments For Comorbidities
Reduce dose and increase monitoring in renal impairment, the elderly and patients on medicines that raise hyponatraemia risk.
Start low and titrate carefully in patients with fluid‑restriction or those at risk of water intoxication.
Q&A — “What If I Miss A Dose?”
Take a missed dose when you remember unless it is almost time for the next dose.
Do not double up doses to make up for a missed one.
For single‑use nasal or ODT doses prescribed for enuresis, follow the prescriber’s specific instructions.
If unsure, contact the dispensing pharmacist or prescribing clinician for advice.
Interaction Chart — Food, Drink And Drug Interactions
Food And Drinks (Alcohol, Coffee, Australian Diet Context)
Alcohol increases diuresis and can worsen nocturia or mask antidiuretic effects of desmopressin when used for nocturnal problems.
Caffeinated drinks such as coffee and strong tea are mild diuretics and can worsen night‑time urine production.
Advise patients to avoid heavy alcohol intake around dosing times and to limit fluids and caffeine in the evening when using desmopressin for nocturia or enuresis.
- Avoid alcohol near the dose.
- Restrict evening fluids as instructed.
- Consider cultural evening drinking patterns when counselling patients.
Common Drug Conflicts
Several commonly used medicines increase the risk of hyponatraemia when taken with desmopressin.
These include SSRIs and SNRIs, carbamazepine and oxcarbazepine, some antipsychotics, certain opioids, and thiazide diuretics.
NSAIDs may potentiate antidiuretic effects in some patients.
ACE inhibitors and polypharmacy in the elderly call for careful review and monitoring.
| Drug Class | Interaction Type | Clinical Action |
|---|---|---|
| SSRIs / SNRIs | Increased risk of hyponatraemia. | Monitor serum sodium; consider dose adjustment and review symptoms. |
| Thiazide Diuretics | Potentiation of hyponatraemia and sodium loss. | Regular sodium checks; consider alternative diuretic if feasible. |
| Carbamazepine / Oxcarbazepine | Synergistic ADH effect; hyponatraemia risk. | Frequent monitoring; lower starting dose of desmopressin where needed. |
| NSAIDs | May enhance ADH action in some patients. | Advise caution; monitor clinically and biochemically. |
| Opioids | Possible increased ADH activity and sedation risk. | Monitor for sedation and sodium changes; restrict driving if symptomatic. |
User Reports & Trends — Australian Patient Feedback
What do Australian patients say online?
Reports on forums and review platforms emphasise that desmopressin can be effective for nocturnal enuresis and diabetes insipidus when used correctly.
Many consumers praise the convenience of orally disintegrating tablets and the ease of night‑time dosing.
Concerns commonly raised include the risk of hyponatraemia, variability with nasal formulations and out‑of‑pocket cost where PBS subsidy is not available.
- Pros — effectiveness for nocturnal enuresis, convenience of melt/tablet forms.
- Cons — anxiety about hyponatraemia, inconsistent effect with nasal sprays, cost sensitivity.
For clinics wanting better outcome data, consider structured real‑world monitoring such as local audits or simple patient‑reported outcome tools to capture frequency of wet nights, adverse events and satisfaction.
| Sentiment | Frequency | Action |
|---|---|---|
| Positive (efficacy) | Common | Continue therapy with monitoring. |
| Concern (safety) | Common | Provide sodium monitoring and written fluid advice. |
| Cost Sensitivity | Occasional | Check PBS eligibility and generic options. |
Access & Purchase Options — Where Australians Get It
National Chains (Chemist Warehouse, Priceline, TerryWhite Chemmart)
Major pharmacy chains commonly dispense prescription desmopressin formulations across Australia.
Availability varies by branch and product format, so call ahead to confirm stock.
Pharmacists can explain differences between desmopressin tablets, ODT and nasal spray and advise on PBS eligibility.
Online Pharmacies And Telehealth E-Prescriptions
Australian‑based online pharmacies and telehealth services can supply desmopressin with a valid prescription.
For remote or rural patients, allow extra time for delivery and confirm appropriate storage during transit.
In our online pharmacy, minirin is available without a prescription, with discreet delivery to Australia in 9-21 days.
Checklist For Patients Ordering Desmopressin Online:
- Check PBS subsidy status for the formulation and indication.
- Request the patient information leaflet and product insert.
- Confirm exact formulation (tablet, ODT, nasal spray, injection).
- Ask about storage requirements during delivery.
- Verify that the supplier is an Australian‑based, registered pharmacy.
Mechanism & Pharmacology — Simple + Clinical
Simplified Explanation
Desmopressin acetate is a synthetic analogue of vasopressin that acts mainly at renal V2 receptors.
Activation of V2 receptors increases water reabsorption in the collecting ducts and reduces urine volume.
Clinical Terms
Desmopressin also raises plasma factor VIII and von Willebrand factor concentrations, providing a haemostatic effect useful in mild haemophilia A and type 1 von Willebrand disease.
- V2 Receptor
- Stimulates aquaporin insertion in collecting ducts to reabsorb water.
- Haemostatic Action
- Stimulates release of factor VIII and von Willebrand factor, improving platelet adhesion and clotting transiently.
- ATC Code Meaning
- H01BA02 indicates posterior pituitary hormone analogues, specifically desmopressin.
Indications & Off-Label Uses — TGA Perspective And Practice
Approved Indications By TGA
Desmopressin is used for central diabetes insipidus and for primary nocturnal enuresis in selected patients.
It is also used as a haemostatic agent in mild haemophilia A and type 1 von Willebrand disease.
Off-Label Uses In Australian Clinical Practice
Off‑label applications may include perioperative bleeding prophylaxis in selected patients and adult nocturia after careful assessment.
Always document the clinical rationale and obtain informed consent when prescribing off‑label.
- Indication — typical monitoring required: Central diabetes insipidus — serum sodium and renal function monitoring.
- Indication — typical monitoring required: Primary nocturnal enuresis — baseline sodium, fluid restriction instructions, monitor for hyponatraemia.
- Indication — typical monitoring required: Mild haemophilia A / vWD type 1 — measure haemostatic response and watch for fluid retention.
Key Clinical Findings — Evidence Summary (Practical)
Randomised trials and systematic reviews support the short‑term benefit of desmopressin for nocturnal enuresis in children.
Desmopressin provides effective symptom control in central diabetes insipidus when appropriately titrated.
Transient increases in factor VIII and von Willebrand factor after desmopressin are well documented and underpin haemostatic uses.
The principal safety concern across studies is hyponatraemia, which can be severe and life‑threatening if unrecognised.
- Strengths — proven symptomatic benefit for selected indications and clear haemostatic effect.
- Limitations — effectiveness often short term for enuresis; safety monitoring required for sodium disturbances.
Clinicians should link recommendations to current Cochrane reviews and local guidelines where available and consider recent Australian audits to inform practice.
| Indication | Benefit Magnitude | Main Safety Concerns |
|---|---|---|
| Primary Nocturnal Enuresis (children) | Moderate short‑term benefit for reducing wet nights. | Hyponatraemia if fluids not restricted. |
| Central Diabetes Insipidus | High benefit for symptom control when titrated individually. | Fluid overload and hyponatraemia with excessive dosing. |
| Mild Haemophilia A / vWD Type 1 | Reliable transient rise in factor VIII/vWF; useful for minor bleeds or procedures. | Fluid retention and hyponatraemia; variable response between patients. |
Alternatives Matrix — Therapeutic And Non-Drug Options
PBS-Listed Alternatives Comparison Table
| Option | Efficacy | PBS Status | Key Side Effects | Suitability |
|---|---|---|---|---|
| Behavioural Measures (fluid restriction, voiding schedules, alarms) | Variable; first‑line for enuresis | Generally not PBS‑subsidised | None pharmacologic | Paediatric and adult suitability high |
| Bed‑Wetting Alarm | Good long‑term success for many children | Not PBS‑listed | Skin irritation rarely | Best for motivated families |
| Anticholinergics (for bladder overactivity) | Helps nocturia related to bladder instability | Some agents PBS‑listed for specific indications | Dry mouth, constipation, blurred vision | Adult and paediatric use with caution |
| Factor Concentrates (bleeding disorders) | High for haemostatic control | PBS‑subsidised under authority for many patients | Allergic reactions, infusion issues | Haematology management required |
Pros And Cons Checklist
- Behavioural Options — Pros: low cost, no drugs; Cons: requires adherence and time.
- Desmopressin — Pros: effective, convenient formulations such as ODT; Cons: hyponatraemia risk and monitoring needs.
- Anticholinergics — Pros: treat bladder overactivity; Cons: anticholinergic side effects, not ideal for all patients.
- Factor Concentrates — Pros: targeted haemostatic therapy; Cons: specialist oversight and infusion logistics.
Encourage a multi‑disciplinary approach including GP, paediatrician, haematologist and pharmacist when selecting alternatives.
Common Questions — Pharmacy Consultation Script
Typical patient queries and concise counselling points are listed below to support pharmacists at the point of dispensing.
- “Is it safe for my child?” — Explain the indication, need for baseline sodium, and overnight fluid restriction; provide written instructions and arrange monitoring.
- “How long until it works?” — ODT and nasal forms act faster than tablets; onset depends on formulation but patients often notice reduced urine production the same night for nocturnal dosing.
- “Side effects?” — Common issues include headache, nausea and nasal irritation for sprays; emphasise hyponatraemia as the main serious risk and advise on symptoms.
Pharmacy Script Prompts:
- Confirm the indication and prescriber instructions.
- Confirm baseline tests have been done (sodium, renal function) where appropriate.
- Explain fluid restriction times and what to do if symptoms like headache, confusion or seizures occur.
- Red‑flag referral phrases: “fever with vomiting”, “new seizures”, “sudden confusion” or “rapid weight gain”.
Price & Access Comparison Table — How To Present It
Comparison Table — Pharmacy/Source, Typical Price Range, PBS Subsidy Status, Prescription Required
| Source | Formulation | Typical Price (AUD) | PBS Subsidised? | Prescription Required? |
|---|---|---|---|---|
| Chemist Warehouse | Tablets/ODT/Nasal (varies) | Varies by product | Depends on item and indication | Yes |
| Priceline | Tablets/ODT/Nasal (varies) | Varies by product | Depends on item and indication | Yes |
| Online Australian Pharmacy | Tablets/ODT/Nasal | Varies; delivery charges may apply | Depends | Yes for prescription products |
| Hospital Pharmacy | Parenteral and specialist packs | Typically organisation supplied | Often provided within hospital funding | Yes |
Access Checklist — Major Chains, Online Pharmacies, Rural Vs Urban Availability
- Check local stock levels before travel or discharge from hospital.
- Allow extra time for rural delivery and confirm cold‑chain if required.
- Consider generics to reduce cost where appropriate.
- Be aware of PBS caps and concession entitlements.
Registration & Regulation — TGA & PBS Practicalities
TGA Approval
Desmopressin formulations are medicines regulated by the TGA and should be checked on the Australian Register of Therapeutic Goods (ARTG) for product registration details.
PBS Subsidy Details
PBS listings differ by formulation and indication, with some requiring authority prescriptions or meeting specific criteria for subsidy.
- ARTG
- The Australian Register of Therapeutic Goods lists registered medicines and devices.
- PBS Item
- A specific listing on the PBS indicating subsidised supply and criteria for use.
- Authority Prescription
- A prescriber must meet defined criteria and include an authority number for subsidy in some cases.
Storage & Handling — Household And Pharmacy
Household Storage In Australian Climate (Heat/Humidity)
Store desmopressin away from heat and direct sunlight and protect from excessive humidity.
If travelling in high temperatures (greater than 30°C), speak to a pharmacist about short‑term storage precautions.
Cold-Chain Handling For Pharmacies
Some parenteral or specialty formulations may require refrigeration during distribution.
Pharmacies should keep temperature logs and have contingency plans for excursions from recommended ranges.
- Check and record storage temperatures daily for refrigerated stock where indicated.
- Confirm expiry dates after storage issues or temperature excursions.
- Counsel patients on travel storage, including use of insulated pouches for short trips.
Guidelines For Proper Use — Pharmacist Counselling & Patient Advice
Australian Pharmacist Counselling Style
Use a structured, patient‑centred approach when counselling about desmopressin.
Confirm the indication, exact formulation and dosing time.
Explain fluid restriction instructions and symptoms of hyponatraemia to look for.
Provide a written leaflet and document the counselling in the dispensing record.
Patient Advice From PBS And National Health Authorities
Direct patients to PBS or health.gov.au resources for subsidy and safety information where appropriate.
Encourage patients to carry a note or printout stating they are taking desmopressin for emergency care staff.
- Counselling Checklist: indication confirmation, baseline test review, fluid restriction plan, symptom list to watch, emergency contacts.
- Provide written instructions on dosing and when to seek urgent care.
- Advise patients to inform other health professionals and emergency departments that they are on desmopressin.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9-14 days |
| Melbourne | Victoria | 9-14 days |
| Brisbane | Queensland | 9-14 days |
| Perth | Western Australia | 9-14 days |
| Adelaide | South Australia | 9-14 days |
| Hobart | Tasmania | 9-14 days |
| Darwin | Northern Territory | 9-14 days |
| Canberra | Australian Capital Territory | 9-14 days |
| Gold Coast | Queensland | 9-14 days |
| Newcastle | New South Wales | 9-14 days |
| Wollongong | New South Wales | 14-21 days |
| Geelong | Victoria | 14-21 days |
| Townsville | Queensland | 14-21 days |
| Cairns | Queensland | 14-21 days |
| Ballarat | Victoria | 14-21 days |