Tamsulosin
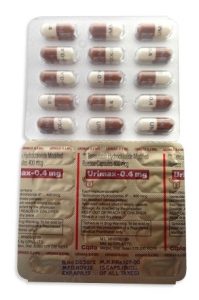
In brief
- In many countries tamsulosin is officially prescription‑only, but in some pharmacies it may be sold without a prescription or receipt — check local regulations and availability in your area.
- Tamsulosin is used to relieve lower urinary tract symptoms (LUTS) due to benign prostatic hyperplasia (BPH); it is a selective alpha‑1A adrenergic antagonist that relaxes smooth muscle in the prostate and bladder neck.
- The usual dose for adult men with BPH is 0.4 mg once daily, taken after the same meal each day (lower 0.2 mg doses are used in some populations or regions).
- Oral administration as modified‑release capsules or tablets (commonly 0.4 mg MR; 0.2 mg formulations also available).
- Some pharmacodynamic effects can occur within hours, but symptomatic relief is typically noticed within a few days and often becomes more apparent over 1–2 weeks.
- Duration of action is approximately 24 hours with once‑daily modified‑release dosing (steady symptomatic control with daily use).
- Avoid or limit alcohol while taking tamsulosin — alcohol can increase the risk of dizziness and low blood pressure (orthostatic hypotension).
- The most common side effect is dizziness, especially on standing (other frequent effects include ejaculatory disorders, headache, nasal congestion and fatigue).
- Would you like to try “tamsulosin” without a prescription?
Critical Warnings, Restrictions And Patient Protection (Australia)
Basic Tamsulosin Information
- INN (International Nonproprietary Name): Tamsulosin.
- Brand Names Available In Australia: Not specified.
- ATC Code: G04CA02.
- Forms & Dosages: 0.4 mg modified‑release capsule/tablet commonly; 0.2 mg available in some regions; combination products with dutasteride exist.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Prescription Only (Rx) in nearly all major regions.
Overview — Immediate Safety Priorities
Tamsulosin can cause symptomatic hypotension, dizziness and syncope, particularly when treatment starts or when other blood‑pressure‑lowering drugs are used.
Prioritise patient protection by ruling out prostate cancer before treating lower urinary tract symptoms (LUTS) attributed to benign prostatic hyperplasia (BPH).
Check for a history of orthostatic hypotension, severe hepatic impairment, or prior hypersensitivity to tamsulosin or excipients.
Flag the risk of intraoperative floppy iris syndrome ahead of any cataract surgery and advise patients to inform their ophthalmologist.
Use a concise screening checklist before supply to reduce avoidable harm.
- Cardiac history — heart failure, arrhythmias, syncope.
- Current antihypertensives — especially alpha blockers, ACE inhibitors, ARBs, diuretics.
- CYP3A4 or CYP2D6 inhibitors — check recent and current medicines.
- Prior eye surgery or planned cataract operation.
Observe frail elderly patients after the first dose or after dose changes where possible and advise standing up slowly from sitting or lying positions.
Advise patients who work at heights or operate heavy machinery to notify their employer and to avoid hazardous tasks until they know how tamsulosin affects them.
High‑Risk Groups (Elderly, Pregnancy, Chronic Illness)
Which patients need extra monitoring and caution when starting tamsulosin?
- Elderly
- Increased orthostatic hypotension risk; monitor blood pressure and consider supervised first‑dose observation for frail patients.
- Severe Renal Impairment
- CrCl <10 mL/min requires caution and closer monitoring; no routine adjustment for mild–moderate impairment.
- Severe Hepatic Impairment
- Tamsulosin is not recommended in severe hepatic impairment.
- Cardiovascular Disease
- Patients with significant cardiac disease should be observed for syncope and drug interactions that lower blood pressure.
- Pediatric / Pregnancy
- Not indicated and contraindicated in children; pregnancy not applicable for the primary indication (adult men with BPH).
Required actions include medication review, baseline blood pressure measurement, and liaison with the GP or urologist where comorbidity complicates therapy.
Interaction With Activities (Driving, Workplace Safety)
Dizziness and fainting are the adverse effects most likely to impair driving or workplace safety with tamsulosin.
Advise patients not to drive or operate heavy machinery until they know how the medicine affects them.
Document counselling in the pharmacy record and, when appropriate, provide a written note for employers recommending temporary work modifications.
Encourage scheduling the first dose at a time when the patient can sit or rest if symptoms occur, for example when at home rather than before a long drive.
Q&A — “Can I Drive After Taking It In Australia?”
Q: Can I drive after my first dose of tamsulosin?
A: No—avoid driving or hazardous tasks for 24–48 hours after the first dose or after a dose increase.
A: If dizziness or light‑headedness occurs at any time, do not drive and seek medical advice.
A: If fainting happens, present to emergency services because syncope can signal significant hypotension.
A: For patients on antihypertensives or with cardiac disease, extend the observation period and discuss fitness to drive with the prescriber.
Usage Basics — INN, Brands And Legal Status In Australia
INN, ATC And Commonly Used Brand Names
International Nonproprietary Name is tamsulosin.
ATC code is G04CA02, classifying it as an alpha‑adrenoreceptor antagonist used for benign prostatic hyperplasia.
Common internationally seen brand names include Flomax, Omnic and generic tamsulosin products.
- INN: Tamsulosin.
- ATC: G04CA02 — Alpha‑1A selective adrenergic antagonist for BPH.
- Formulation Types: Modified‑release oral capsules/tablets (0.4 mg) and lower‑dose 0.2 mg formulations in some regions.
| INN | ATC | Main Brands |
|---|---|---|
| Tamsulosin | G04CA02 | Flomax, Omnic, Generic 0.4 mg MR |
Legal Classification (TGA, PBS)
Tamsulosin is a prescription‑only medicine in most jurisdictions.
It is registered with national regulators in many regions, but confirmation of TGA registration should be sought via official databases for local labelling and use.
PBS subsidy status can change and prescribers should check the current PBS Schedule and authority codes before claiming subsidy.
- Checklist for Prescribers: Confirm TGA label indication.
- Checklist for Prescribers: Check PBS criteria and authority requirements.
- Checklist for Prescribers: Document clinical rationale in the patient record before applying for subsidy.
Dosing Guide And Administration
Standard Regimen And Practical Advice
The standard adult dose for BPH is 0.4 mg once daily taken after the same meal each day to reduce orthostatic effects.
Lower 0.2 mg formulations exist in some regions but 0.4 mg MR is the most common formulation worldwide.
Adherence matters — taking tamsulosin at a consistent time daily helps stabilise symptoms and plasma levels.
- Take after a meal, at the same time each day.
- Do not crush or chew modified‑release capsules or tablets.
- If changing brands, confirm formulation is MR/OCAS equivalent before advising substitution.
Example patient scenario: a man who takes tamsulosin after breakfast notices fewer nocturia episodes after two weeks when dosing timing is consistent.
Adjustments For Comorbidities And Special Populations
Children and adolescents should not be given tamsulosin as safety and efficacy are not established.
Elderly patients do not require routine dose reduction but need closer monitoring for hypotension and syncope.
Mild to moderate renal impairment does not generally need dosage adjustment, but severe renal impairment (CrCl <10 mL/min) requires caution.
Mild to moderate hepatic impairment usually does not need adjustment, but severe hepatic impairment is not recommended.
Coordinate with the GP or urologist when patients are on multiple antihypertensives or potent CYP3A4/CYP2D6 inhibitors.
Q&A — “What If I Miss A Dose?”
Q: Missed a dose — what should I do?
A: Take the missed dose as soon as you remember unless it is close to the time for the next dose.
A: Do not double up doses to make up for a missed one.
A: If vomiting or overdose occurs, seek urgent medical attention due to the risk of hypotension and syncope.
A: Keep dosing consistent with food to lower the chance of symptomatic side effects after missed doses are resumed.
Interaction Chart — Food, Drink And Drug Interactions
Food And Drink Considerations (Australian Context)
Alcohol can worsen dizziness and orthostatic hypotension when combined with tamsulosin and should be used with caution.
There are no major food interactions documented, but taking the dose after the same meal each day stabilises absorption.
In rural and remote areas where travel distances are long and reliance on driving is high, advise dosing at times that avoid being on the road soon after taking the medicine.
Common Drug Interactions And Clinical Action
Key medicine interactions require pharmacist review before supply.
| Drug / Class | Risk | Recommended Action |
|---|---|---|
| CYP3A4 inhibitors (e.g. ketoconazole) | Increased tamsulosin exposure | Monitor closely; consider alternative or dose review |
| CYP2D6 inhibitors (e.g. fluoxetine) | Increased tamsulosin exposure | Monitor for hypotension; liaise with prescriber |
| Antihypertensives (ACEi, ARB, diuretics) | Increased risk of hypotension and syncope | Monitor BP; consider staged dosing or review regimen |
| PDE5 inhibitors (e.g. sildenafil) | Combined hypotensive effects | Advise caution; monitor symptoms when treatment started together |
Recommend a pharmacist‑led medication review whenever a new prescription is started that could interact with tamsulosin.
User Reports, Trends And Patient Experience (Australia)
What patients commonly tell pharmacists about tamsulosin in Australia.
- Improved urinary flow and reduced LUTS symptoms over days to weeks.
- Initial light‑headedness or dizziness, often resolving within 1–2 weeks.
- Ejaculatory changes such as reduced or absent ejaculation reported by some men.
- Fatigue and occasional headaches noted in consumer feedback.
- Concerns about cataract surgery and “floppy iris” mentioned at pre‑surgery counselling.
- Reduced adherence when patients live rurally and rely on mail delivery without scheduled follow‑up.
Short quote‑style summary: “Many men notice flow improvement within days, but some are surprised by dizziness or ejaculation changes and need reassurance.”
Clinicians should set expectations at the point of dispensing and arrange follow‑up at 2–4 weeks, especially for telehealth or rural patients where adherence and observation may be lower.
Access And Purchase Options In Australia
National Pharmacy Chains And Community Access
Major Australian outlets commonly dispense tamsulosin through community pharmacies including Chemist Warehouse, Priceline and TerryWhite Chemmart.
Availability of branded versus generic formulations varies between chains and individual pharmacy stock lists influence substitution at dispensing.
| Chain | Typical Service | Notes |
|---|---|---|
| Chemist Warehouse | In‑store supply, home delivery | Often price competitive; generic stock varies by store |
| Priceline | In‑store supply, delivery options | Pharmacy counselling available; stock dependent |
| TerryWhite Chemmart | In‑store supply, home delivery | Strong community pharmacy network for follow‑up |
| Independent Pharmacies | In‑store supply, local delivery | Personalised counselling and medication reviews |
In our online pharmacy, tamsulosin is available without a prescription, with discreet delivery to Australia in 9‑21 days.
Online Pharmacies, Telehealth And Rural Access
E‑prescriptions issued via telehealth are commonly accepted by Australian pharmacies and many online pharmacies offer home delivery or parcel‑locker options.
Rural patients may face delayed access and should arrange early repeat prescriptions and community nurse or pharmacist liaison to prevent gaps in therapy.
- Access Checklist For Patients: Bring a current medication list and clarify PBS authority if needed.
- Access Checklist For Patients: Ask about mail‑order timelines and delays during hot weather.
- Access Checklist For Patients: Consider scheduling a phone check‑in at 2 weeks to review symptoms and blood pressure.
Mechanism Of Action And Pharmacology (Clear, Concise)
Simplified Explanation For Patients
Tamsulosin selectively blocks alpha‑1A adrenoceptors in the prostate and bladder neck.
This relaxes the smooth muscle in those areas, making it easier to pass urine and reducing symptoms of urinary obstruction.
In plain language: it relaxes the tube from the bladder to the penis so urine flows more easily.
- Receptor: Alpha‑1A adrenoceptor.
- Location: Prostate and bladder neck.
- Effect: Smooth muscle relaxation and improved urinary flow.
Clinical Pharmacology Notes For Clinicians
Modified‑release 0.4 mg once‑daily dosing is designed to provide steady plasma levels and once‑daily convenience.
Metabolism involves CYP pathways, so potent CYP3A4 or CYP2D6 inhibitors can raise systemic exposure.
Therapeutic role is symptomatic relief of LUTS due to BPH rather than reducing prostate size.
- Symptomatic relief typically seen within days to weeks.
- No meaningful reduction in prostate volume with monotherapy.
- Monitor for ejaculatory dysfunction and orthostatic hypotension.
Indications And Off‑Label Use
TGA‑Approved Indications
Primary indication is relief of lower urinary tract symptoms associated with benign prostatic hyperplasia in adult men.
It is not indicated for hypertension, erectile dysfunction or routine use in women.
Supply should follow labelled indications and local regulatory guidance.
Off‑Label Considerations In Australian Practice
Off‑label uses for tamsulosin are uncommon in practice for BPH indications.
Combination therapy with a 5‑alpha‑reductase inhibitor such as dutasteride is used for larger prostates and to reduce long‑term progression, and combination products exist internationally.
- Pros: Faster symptom relief with alpha blocker and long‑term prostate reduction with 5‑ARI in combination.
- Cons: Increased sexual side effects, higher cost, and PBS criteria may restrict subsidy.
Always document clinical justification and obtain informed consent when prescribing outside standard monotherapy pathways.
Key Clinical Findings And Evidence Summary (2022–2026 Focus)
Recent evidence continues to support the efficacy of alpha‑1A selective agents for symptomatic improvement in LUTS with a generally lower orthostatic risk than older non‑selective alpha blockers.
Combination therapy with a 5‑alpha‑reductase inhibitor shows improved outcomes for larger prostates and can reduce the risk of clinical progression over years.
Sexual adverse effects, particularly ejaculatory disturbances, are more commonly reported with highly selective agents like tamsulosin and silodosin.
- Primary Endpoints: IPSS reduction and improvements in peak urinary flow (Qmax).
- Monotherapy: Rapid symptom relief but no prostate shrinkage.
- Combination Therapy: Better long‑term progression prevention for larger prostates.
| Outcome | Monotherapy | Combination (Alpha Blocker + 5‑ARI) |
|---|---|---|
| Symptom Improvement | Good within days–weeks | Good plus long‑term maintenance |
| Prostate Size | No significant reduction | Reduced over months |
| Sexual Side Effects | Possible ejaculatory changes | Higher incidence when combined |
Alternatives Matrix — PBS‑Listed Drugs And Comparisons
Comparison Table (Recommended)
| Drug | Class | Typical Benefit | Main Adverse Effects | PBS Status |
|---|---|---|---|---|
| Alfuzosin | Non‑selective alpha‑1 antagonist | Symptom relief with less selectivity | Orthostatic hypotension, dizziness | Varies — check PBS |
| Silodosin | Highly selective alpha‑1A antagonist | Strong symptom relief | High rate of ejaculatory dysfunction | Varies — check PBS |
| Doxazosin | Alpha‑1 antagonist with antihypertensive action | Useful where BPH and hypertension coexist | Hypotension, dizziness | Varies — check PBS |
| Finasteride | 5‑alpha‑reductase inhibitor | Reduces prostate size over months | Sexual dysfunction, decreased libido | Varies — check PBS |
| Dutasteride | 5‑alpha‑reductase inhibitor | Dual enzyme inhibition, reduces prostate size | Sexual dysfunction | Varies — check PBS |
Pros And Cons Checklist For Prescribers
- Consider symptom profile: storage versus voiding symptoms when choosing an alpha blocker or a 5‑ARI.
- Check prostate size: finasteride/dutasteride indicated for larger prostates to reduce progression risk.
- Comorbid Hypertension: doxazosin may be useful but watch additive hypotension.
- Sexual Side‑Effect Priorities: silodosin and combination therapies have higher ejaculatory dysfunction rates.
- Drug Interactions: verify CYP inhibitors and concurrent antihypertensive therapy.
- PBS Access: check subsidy criteria as it may influence choice and affordability.
Common Questions And Pharmacy Counselling Points
Top questions seen in Australian practice and succinct counselling scripts for pharmacists.
- Onset Of Effect: “You may notice improvement within days, but give it a few weeks for full effect.”
- Sexual Side Effects: “Some men report reduced or absent ejaculation; let your GP know if this is troublesome.”
- Dizziness Precautions: “Stand up slowly and avoid driving for 24–48 hours after starting or changing dose.”
- Cataract Surgery Warning: “Inform your ophthalmologist before eye surgery as tamsulosin is linked with floppy iris syndrome.”
- Storage Advice: “Store in original packaging below 25°C, away from moisture and heat.”
Short pharmacist scripts for dispensing: “Take 0.4 mg after the same meal each day; stand slowly; if you feel dizzy stop driving and contact your GP.”
Document counselling in the dispensing notes and schedule follow‑up at 2–4 weeks to check symptom response and blood pressure.
Price & Access Comparison (Pharmacy/Source, PBS Status)
Suggested Table Structure For Web Content
| Pharmacy / Source | Typical Price Range (Cash) | PBS Subsidy Available | Prescription Required | Delivery Options |
|---|---|---|---|---|
| Chemist Warehouse | Varies by brand | Verify PBS | Yes | In‑store, home delivery |
| Priceline | Varies by brand | Verify PBS | Yes | In‑store, delivery |
| TerryWhite Chemmart | Varies by brand | Verify PBS | Yes | In‑store, home delivery |
| Major Online Pharmacies | Varies; often competitive | Verify PBS | Yes | Home delivery, parcel locker |
| Clinic Dispensaries | Varies | Verify PBS | Yes | Immediate collect or arranged delivery |
Access Checklist (Rural Versus Urban)
- Check PBS authority rules before prescribing or dispensing.
- Allow time for mail delivery, particularly in summer months.
- Confirm local stock before travel if the patient is away from home.
- Consider early repeats and community pharmacist liaison for remote patients.
- Be mindful of cost sensitivity and emphasise pharmacist counselling as trusted primary support.
Registration, Regulation And Prescribing In Australia
TGA Registration And Oversight
Tamsulosin is regulated as a prescription medicine in most countries and should follow the TGA‑approved Product Information and Consumer Medicines Information in Australia when labelled locally.
Regulatory activities include registration, labelling approval and post‑market surveillance for adverse events.
- Registration: Application for market authorisation with supporting clinical data.
- Labelling: Approved Product Information guides dosing and safety messages.
- Post‑Market Surveillance: Ongoing adverse event reporting and risk‑management.
PBS Subsidy And Prescriber Responsibilities
PBS listing and authority requirements vary and prescribers must meet clinical criteria to claim subsidies.
Keep records of clinical justification and use authority codes where required to ensure correct subsidy application and audit readiness.
Pharmacists should verify prescriptions, discuss PBS options with patients and document any counselling about cost or access alternatives.
Storage, Transport And Handling (Household & Pharmacy)
Household Storage In Australian Climate
Store tamsulosin below 25°C in the original packaging and away from moisture and direct heat, which is important during hot Australian summers.
Avoid storing in bathrooms or near kitchen sinks and keep all medicines out of reach of children.
Dispose of expired or unwanted stock via pharmacy‑run medicine take‑back programs.
- Cool, dry place away from sunlight.
- Do not store in the bathroom due to humidity.
- Keep blister pack intact until required.
Pharmacy Cold‑Chain And Transport Considerations
Modified‑release capsules do not require cold chain but avoid prolonged exposure to excessive heat during transport.
Use insulated packs for mailings during summer and check returned product integrity if temperature excursions are suspected.
Pharmacies should record batch numbers and expiry dates and follow TGA guidance on storage and transport.
Guidelines For Proper Use — Counselling And Follow‑Up
Australian Pharmacist Counselling Style
Start counselling with the patient’s main concern or question to make the conversation relevant.
Explain once‑daily MR dosing of 0.4 mg after the same meal, warn about dizziness and ejaculatory changes, and explain missed‑dose rules.
Advise informing ophthalmologists prior to any eye surgery because of the floppy iris risk.
- Confirm indication and review the medication list for interactions.
- Obtain baseline blood pressure where possible.
- Arrange a follow‑up call or clinic review at 2–4 weeks to assess response and tolerability.
- Discuss PBS options and costs with the patient.
Patient Follow‑Up And When To Seek Care
Ask patients to seek urgent care for fainting, severe dizziness, signs of angioedema or severe allergic reactions.
Recommend urological review for persistent or worsening LUTS, haematuria or suspicion of prostate cancer.
Document counselling and arrange medication review when co‑prescribed antihypertensives or potent CYP inhibitors.
- Emergency Signs: Syncope, severe shortness of breath, facial swelling or widespread rash.
- Routine Monitoring: Blood pressure checks and symptom score review at 2–4 weeks.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9–14 days |
| Melbourne | Victoria | 9–14 days |
| Brisbane | Queensland | 9–14 days |
| Perth | Western Australia | 9–14 days |
| Adelaide | South Australia | 9–14 days |
| Canberra | Australian Capital Territory | 9–14 days |
| Hobart | Tasmania | 9–14 days |
| Darwin | Northern Territory | 14–21 days |
| Gold Coast | Queensland | 9–14 days |
| Newcastle | New South Wales | 9–14 days |
| Wollongong | New South Wales | 14–21 days |
| Townsville | Queensland | 14–21 days |
| Cairns | Queensland | 14–21 days |