Fulnite
In brief
- Fulnite is sold in pharmacies and via online suppliers in countries where it is marketed (listed in India as Fulnite); it is legally a prescription‑only medicine (Rx) in most markets, although some pharmacies or online sellers may supply it without a prescription — purchasing without a prescription is not recommended and local law varies.
- Fulnite (eszopiclone) is used to treat insomnia; it is a non‑benzodiazepine sedative‑hypnotic that acts at GABA‑A receptors to help reduce time to sleep and improve sleep maintenance.
- The usual adult dose is 1 mg at bedtime, with possible increase to 2 mg or 3 mg if needed and tolerated (maximum 3 mg/day); elderly patients should start at 1 mg; not recommended for children; typical short‑term treatment is 2–4 weeks.
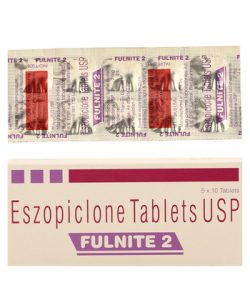
- Fulnite is administered orally as film‑coated tablets, commonly available in 1 mg, 2 mg and 3 mg strengths (often blister packs in some markets).
- The effect usually begins within about 15–30 minutes; it should be taken only when you can get a full night’s sleep (around 7–8 hours).
- Duration of action is typically around 6–8 hours, though some people may experience next‑day drowsiness or impaired coordination.
- Do not consume alcohol while taking fulnite — alcohol markedly increases sedation, cognitive impairment and the risk of respiratory depression.
- The most common side effects include a bitter or metallic taste, dry mouth, headache, dizziness and next‑day drowsiness or confusion.
- Would you like to try fulnite without a prescription?
Safety, Warnings And Patient Protection (Australia)
Basic Fulnite Information
- INN (International Nonproprietary Name): Eszopiclone.
- Brand Names Available In Australia: Lunesta (internationally), Fulnite (India/Asia), generic eszopiclone; local availability and brand presence vary and should be checked against the TGA ARTG.
- ATC Code: N05CF04.
- Forms & Dosages: Tablets 1 mg, 2 mg and 3 mg; common packaging includes blister packs and bottles.
- Manufacturers In Australia: Not specified; global suppliers include Sepracor/Sunovion, Sun Pharma, Intas and multiple generic manufacturers.
- Registration Status In Australia: Not specified; check TGA ARTG for current registration details.
- OTC / Rx Classification: Prescription only (Rx) in all markets per current product information.
Worried about safety or whether eszopiclone is right for you?
Eszopiclone (often sold as Fulnite or Lunesta elsewhere) is a prescription‑only hypnotic with important safety considerations for certain patients.
Absolute contraindication is known hypersensitivity to the drug or any excipients.
Relative contraindications and higher‑risk situations need careful clinical assessment before prescribing or dispensing.
High‑Risk Groups (Elderly, Pregnancy, Chronic Illness)
These patients often show greater sensitivity to sedative effects and adverse outcomes.
- Absolute Contraindication: Known hypersensitivity to eszopiclone or formulation ingredients.
- Relative Contraindications: Severe hepatic impairment; significant respiratory depression; untreated sleep apnoea; active substance use disorder; pregnancy and lactation.
- Children: Safety and efficacy are not established — do not use in children.
Checklist For Monitoring Points:
- Start elderly or frail patients at 1 mg and reassess for next‑day sedation, cognitive changes and falls.
- In liver or kidney impairment, limit dose to 1 mg and review frequently for accumulation or prolonged effects.
- For anyone with respiratory disease or sleep apnoea, avoid or use only with specialist oversight.
- Review duration regularly and plan for short courses (2–4 weeks) wherever possible to reduce dependence risk.
Interaction With Activities (Driving, Workplace Safety Under Australian Law)
Driving or operating heavy machinery after taking eszopiclone can be dangerous.
Non‑benzodiazepine hypnotics have been associated with next‑day impairment and complex sleep‑related behaviours such as sleep‑driving.
Australian workplace policies commonly treat sedative use as a fitness‑for‑duty issue for safety‑critical roles.
Advise patients to tell their employer if they perform safety‑sensitive work and are prescribed a sedative.
Q&A — “Can I Drive After Taking It In Australia?”
Q: Can I drive after taking eszopiclone/Fulnite?
A: No — do not drive or operate machinery until you have had a full night’s sleep (7–8 hours) and are confident you have no residual drowsiness.
If you notice next‑day sedation, dizziness or cognitive impairment, avoid driving and contact your pharmacist or GP for advice.
Usage Basics
INN, Brand Names Available In Australia
Eszopiclone is the International Nonproprietary Name used worldwide.
International brands include Lunesta (popular in North America and Europe) and Fulnite (used in India and some Asian markets).
In Australia, clinicians commonly prescribe zopiclone (Imovane) or zolpidem, and eszopiclone availability depends on local registration and supplier arrangements.
- Eszopiclone — INN.
- Lunesta — international brand.
- Fulnite — brand in India/Asia; packaging often blistered tablets.
- Note: Check the TGA ARTG for up‑to‑date local brand listings.
Legal Classification (TGA Approval, PBS Listing)
Eszopiclone is classified as prescription‑only in all markets according to available product information.
TGA registration and PBS subsidy status may change; clinicians and patients must verify current ARTG and PBS entries before prescribing or purchasing.
Eszopiclone has not been a widely PBS‑listed hypnotic historically, so private script costs may apply if it is not subsidised.
Pharmacists can advise on ARTG status, therapeutic alternatives and possible special access pathways such as S100 if appropriate.
| TGA Status | PBS Status | Local Brand Availability |
|---|---|---|
| Not specified — check ARTG | Not specified — historically limited | Variable; Lunesta/Fulnite/generics depend on registration |
Dosing Guide
Standard Regimens (PBS Reference Dosing)
Patients commonly ask what dose to start and how quickly it can be increased.
Standard adult initiation is 1 mg taken at bedtime.
If 1 mg is ineffective and tolerated, clinicians may increase to 2 mg or 3 mg after review.
Typical treatment duration is short term — 2 to 4 weeks — with regular clinical review to reduce tolerance and dependence risks.
- Take at bedtime immediately before lights out.
- Ensure ability to sleep for 7–8 hours to avoid next‑day sedation.
- Start elderly or frail patients at 1 mg and reassess before any escalation.
Checklist For Dose Escalation Criteria:
- Persistent, clinically significant insomnia after an adequate trial of 1 mg.
- No unacceptable side effects at 1 mg (no cognitive blunting or marked next‑day sedation).
- Patient understands dependence risks and agrees to short course with review.
Adjustments For Comorbidities
Special populations need dose rationale and close monitoring.
- Elderly And Frail
- Start 1 mg due to increased sensitivity and fall risk; only increase if well tolerated.
- Liver Or Renal Impairment
- Limit starting dose to 1 mg and monitor for prolonged sedation because metabolism may be slower.
- Respiratory Disorders Or Sleep Apnoea
- Avoid or use only under specialist oversight because of the risk of respiratory depression.
- History Of Substance Use
- Consider non‑drug options such as CBT‑I and obtain addiction risk assessment before prescribing.
Q&A — “What If I Miss A Dose?”
Q: Missed bedtime dose — what do I do?
A: Skip the missed dose; do not double up.
Only take the medication if you can get a full night’s sleep (7–8 hours) after dosing.
If insomnia persists, review with your GP rather than taking extra daytime doses that cause sedation.
Interaction Chart (Food, Drink And Medicines)
Food And Drinks (Alcohol, Coffee, Australian Diet Context)
Common patient concerns include whether they can drink alcohol or have coffee in the evening.
Alcohol and eszopiclone have additive central nervous system depressant effects and should be avoided for at least 24 hours after dosing.
Caffeine does not directly alter eszopiclone pharmacokinetics but will counteract sleep efficacy; advise avoidance of late‑evening caffeine.
High‑fat meals may delay the onset of effect and reduce perceived efficacy for sleep onset.
| Interaction | Severity |
|---|---|
| Alcohol | Major |
| Caffeine (coffee, tea) | Minor |
| High‑fat meal | Moderate |
Common Drug Interactions
Patients often take other medicines that increase sedation or alter liver metabolism.
Major interactions occur with other CNS depressants including opioids, benzodiazepines, antipsychotics and some anticonvulsants.
Strong CYP3A4 inhibitors or inducers can change eszopiclone levels and require dose review.
SSRIs and other antidepressants may increase sedation and should be counselled on when starting or changing doses.
| Drug | Interaction Type | Clinical Action |
|---|---|---|
| Opioids / Benzodiazepines | Additive CNS depression | Avoid combination or use extreme caution; consider alternative therapy |
| Strong CYP3A4 Inhibitors | Increased eszopiclone exposure | Consider dose reduction and monitor |
| SSRIs / Antidepressants | Increased sedation | Advise caution when combined; monitor daytime function |
Perform medicine reconciliation at each prescription renewal and review all sedatives with the pharmacist.
User Reports & Trends (Australian Patient Feedback)
What do Australian patients say about using eszopiclone or related hypnotics?
Feedback commonly includes improved sleep onset and maintenance for many patients, balanced against certain side effects that affect adherence.
- Positive: Faster sleep onset, fewer nighttime awakenings, improvement in sleep duration for short courses.
- Adverse: Bitter or metallic taste in the mouth, next‑day drowsiness, dizziness, and occasional memory complaints.
- Tolerance: Some users report reduced effectiveness after prolonged use, pointing to dependence and tolerance concerns.
- Access Issues: Price sensitivity and limited PBS access can reduce adherence; rural patients report challenges accessing specialist review for dose changes.
| Setting | Reported Trend |
|---|---|
| Urban | Better access to follow‑up; quicker switches to alternatives when side effects occur |
| Rural | Longer waits for GP/specialist review; shipment delays and cost concerns |
Suggest patients keep a sleep diary recording sleep times, daytime function and any adverse effects for GP or pharmacist review.
Access & Purchase Options In Australia
National Chains (Chemist Warehouse, Priceline, TerryWhite Chemmart)
A prescription is required for eszopiclone according to product information.
Major chains may supply branded or generic options depending on stock and registration status.
Pharmacists can recommend therapeutic alternatives such as zopiclone (Imovane) or temazepam where appropriate and advise on cost differences.
Online Pharmacies And Telehealth E‑Prescriptions
Telehealth and e‑prescribing can streamline repeat prescriptions and remote patient follow‑up.
Verify legitimate pharmacy registration and the authenticity of e‑prescriptions before ordering medications online.
Rural patients can use home delivery but should consider secure storage and schedule local medication reviews.
Checklist For Buying Safely Online:
- Verify pharmacy registration and contact details.
- Confirm prescription authenticity and prescriber identity.
- Check delivery times and shipping conditions to protect medication integrity.
- Ensure packaging and storage advice are provided for hot Australian summers.
Mechanism & Pharmacology
Simplified Explanation
Eszopiclone is a non‑benzodiazepine sedative‑hypnotic that modulates GABA‑A receptor activity to increase inhibitory neurotransmission and promote sleep onset and maintenance.
Although structurally different from benzodiazepines, it shares similar receptor target effects that produce sedation.
Clinical Terms (Pharmacokinetics & Dynamics)
Onset is typically rapid when the drug is taken at bedtime.
The elimination half‑life at higher doses can contribute to next‑day effects in some patients.
Hepatic metabolism is involved, so impaired liver function may slow clearance and increase exposure.
- GABA‑A Agonist
- Mediates sedative effects by enhancing inhibitory neurotransmission.
- Onset
- Rapid when taken at bedtime; timing affects efficacy for sleep onset.
- Half‑Life
- Variable with dose; longer exposure increases the chance of next‑day sedation.
- Tolerance And Dependence
- Risk increases with prolonged use beyond recommended short courses.
Check clinical pharmacology summaries and TGA ARTG entries for up‑to‑date pharmacokinetic figures.
Indications & Off‑Label Uses
Approved Indications By TGA (And Typical)
Primary indication is short‑term treatment of insomnia to improve sleep onset and maintenance.
Recommended starting dose is 1 mg at bedtime with possible increase to 2–3 mg for adults when tolerated.
Usual recommended duration is 2–4 weeks, and continued use beyond this should prompt reassessment for dependency and alternative strategies.
Confirm TGA registration and product‑specific indications via ARTG when prescribing or dispensing locally.
Off‑Label Uses In Australian Clinical Practice
Prescribing eszopiclone off‑label for chronic insomnia or complex psychiatric comorbidity should be cautious because of dependence risks.
Non‑pharmacological approaches such as cognitive behavioural therapy for insomnia (CBT‑I) and sleep hygiene are preferred first‑line options.
Checklist For Off‑Label Prescribing:
- Document indication rationale and discuss risks versus benefits with the patient.
- Obtain informed consent and provide a clear monitoring schedule.
- Plan a defined review date and strategy for tapering or stopping the drug.
Key Clinical Findings (Evidence Summary 2022–2026)
Patients and clinicians want a succinct summary of the evidence for benefit and harm.
- Efficacy: Clinical trials and meta‑analyses report improved sleep latency and total sleep time compared with placebo, with small‑to‑moderate effect sizes over short‑term studies (2–4 weeks).
- Adverse Events: Commonly reported effects include bitter/metallic taste, dry mouth, dizziness and next‑day drowsiness.
- Special Populations: Older adults have documented increased fall risk and cognitive impairment; start low and monitor closely.
- Comparative Data: Trials versus zolpidem and zopiclone indicate broadly similar efficacy with differences in side‑effect profiles.
Clinicians should consult TGA, NHMRC and PBS resources for region‑specific guidance and more recent publications.
Alternatives Matrix
PBS‑Listed Alternatives Comparison Table
| Drug / CBT‑I | On‑Label Use | PBS Subsidy Status | Pros | Cons |
|---|---|---|---|---|
| Zopiclone (Imovane) | Short‑term insomnia | Varies; commonly used and may be PBS‑listed in certain indications | Effective for sleep onset and maintenance | Dependence risk; next‑day effects possible |
| Zolpidem | Short‑term insomnia | Varies | Rapid onset | Tolerance and rebound insomnia risk |
| Temazepam | Short‑term severe insomnia | Varies | Strong hypnotic effect | Benzodiazepine dependence; daytime sedation |
| CBT‑I | First‑line for chronic insomnia | Not a PBS drug but accessible via health services | Durable benefit; no pharmacologic side effects | Requires time and access to trained providers |
Pros And Cons Checklist
- Consider patient age and comorbidity when choosing a hypnotic.
- Assess dependence risk and daytime functioning needs.
- Factor cost and PBS status into decision making, especially for long courses.
- Prefer non‑pharmacological measures like CBT‑I where feasible.
Common Questions (Australian Pharmacy Consultations)
Patients often bring a short list of urgent questions to the pharmacy counter.
- Will it make me addicted? Dependence risk increases with prolonged use; review regularly and use short courses where possible.
- Can I drink alcohol? No; avoid alcohol for at least 24 hours after dosing due to additive CNS depression.
- Is it safe in older people? Use lower starting doses (1 mg) and monitor closely for falls and cognitive impairment.
- How long until it works? Usually the same night when taken correctly at bedtime.
Bring a current medication list and a sleep log to consultations and report adverse effects promptly to your GP or pharmacist.
Price & Access Comparison (Table & Checklist)
Comparison Table — Pharmacy/Source, Typical Price Range, PBS Subsidy Status, Prescription Required
| Supplier | Brand/Generic Availability | Typical Retail Price (Private Script) | PBS Subsidy | Prescription Required |
|---|---|---|---|---|
| Chemist Warehouse | Depends on stock; generics possible | Not specified | Not specified | Yes |
| Priceline | Depends on stock | Not specified | Not specified | Yes |
| TerryWhite Chemmart | Depends on stock | Not specified | Not specified | Yes |
| Online Pharmacies | May source generics or imports | Not specified | Not specified | Yes — verify e‑prescription |
Note: Prescription‑only status is indicated in product information; verify PBS listing and prices with your pharmacist.
Access Checklist — Major Chains, Online Pharmacies, Rural Vs Urban Availability
- Check TGA ARTG for registered brands and formulations.
- Ask your pharmacist about therapeutic substitutions if your usual brand is unavailable.
- Consider telehealth for repeat prescriptions if local GP access is limited.
- Compare private script costs across pharmacies and confirm delivery times for rural addresses.
Registration & Regulation (TGA & PBS Practical Steps)
TGA Approval
Always verify current TGA ARTG registration for specific brands such as Lunesta, Fulnite or generic eszopiclone before supply.
If a product is not ARTG‑listed, importation or special access pathways may be required and must be discussed with the prescriber and pharmacist.
PBS Subsidy Details
PBS subsidy status can change and eszopiclone has not been a common PBS‑listed hypnotic historically.
For subsidised options, discuss PBS‑listed alternatives with your GP or pharmacist and consider authority prescriptions where applicable.
- Check the TGA ARTG for brand registration.
- Check the PBS schedule for subsidy status.
- Consult your pharmacist about alternatives and access pathways.
- Consider private scripts or special access if ARTG/PBS options are not suitable.
Storage & Handling (Australian Climate & Pharmacy Practice)
Household Storage In Australian Climate (Heat/Humidity)
Store eszopiclone at 20–25°C and protect tablets from moisture and direct light.
In hot or humid Australian regions avoid storing medicines in bathrooms; choose a cool, dry cupboard away from sunlight.
Keep medicines in their original blister packs or bottles and out of reach of children and pets.
Cold‑Chain Handling For Pharmacies
No cold chain is required for eszopiclone, but pharmacies should maintain air‑conditioned dispensary storage and document temperature monitoring.
For mailed prescriptions, use packaging that shields products from heat and include patient advice on safe storage at home.
- Ideal household storage: cool, dry, dark place away from children.
- Transport tips: avoid leaving medication in hot cars during summer.
- Child‑safety: keep in locked cabinet or high shelf and in original packaging.
Guidelines For Proper Use (Pharmacist Counselling & National Advice)
Australian Pharmacist Counselling Style
Counselling should be clear, direct and focused on patient safety and adherence.
Key counselling points include dose and timing, the need for 7–8 hours sleep, and avoidance of alcohol and other sedatives.
Tell patients to report common side effects such as bitter taste, dizziness or next‑day sedation.
Emphasise that tablets should not be split or chewed unless the product information allows it.
Encourage a sleep diary and arrange review if medication is being used beyond 2–4 weeks.
Patient Advice From PBS And National Health Authorities
National advice favours non‑pharmacological measures such as CBT‑I, sleep hygiene and stimulus control as first‑line for chronic insomnia.
Provide written information, local referral options (sleep clinics, mental health services) and clear instructions for stopping or tapering medication to reduce rebound insomnia.
- Take medication immediately at bedtime when ready to sleep.
- Maintain consistent sleep‑wake times and sleep hygiene measures.
- Keep a sleep diary and bring it to your GP or pharmacist review.
Patient Handout Template: Brief dose, key warnings, side effects to report, emergency contact and follow‑up date for review.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 9–14 days |
| Melbourne | Victoria | 9–14 days |
| Brisbane | Queensland | 9–14 days |
| Perth | Western Australia | 9–14 days |
| Adelaide | South Australia | 9–14 days |
| Hobart | Tasmania | 9–14 days |
| Canberra | Australian Capital Territory | 9–14 days |
| Gold Coast | Queensland | 9–14 days |
| Newcastle | New South Wales | 9–14 days |
| Wollongong | New South Wales | 14–21 days |
| Geelong | Victoria | 14–21 days |
| Townsville | Queensland | 14–21 days |
| Darwin | Northern Territory | 14–21 days |
| Cairns | Queensland | 14–21 days |
Final Notes On Purchase And Availability
Eszopiclone is prescription‑only according to product data; confirm prescription requirements before ordering online.
Our online pharmacy can advise about delivery times and legitimate e‑prescriptions and will assist with safe, discreet packaging and shipping.
Summary And Practical Tips
Eszopiclone (eszopiclone/Fulnite/Lunesta) is a non‑benzodiazepine hypnotic used for short‑term management of insomnia with a usual starting dose of 1 mg at bedtime.
Assess patient suitability carefully in the elderly, in those with hepatic or renal impairment, respiratory disease, pregnancy or history of substance use.
Avoid alcohol and other sedatives while using eszopiclone and do not drive until you are certain there is no next‑day impairment.
Prefer non‑pharmacological treatments such as CBT‑I for chronic insomnia and limit pharmacological therapy to the shortest effective duration with regular review.
Always check TGA ARTG and PBS listings for current registration and subsidy information and consult your pharmacist for personalised advice and medicine reconciliation.