Noroxin
In brief
- In our pharmacy you can buy noroxin without a prescription or receipt, with delivery available across Australia in discreet packaging.
- Noroxin (norfloxacin) is used to treat bacterial infections such as uncomplicated and complicated urinary tract infections, prostatitis and some cases of gonorrhoea; it is a fluoroquinolone antibiotic that works by inhibiting bacterial DNA gyrase and topoisomerase IV, blocking DNA replication and killing bacteria.
- The usual adult dose is 400 mg orally every 12 hours for most UTIs (typically 3–7 days for uncomplicated UTI, 7–10 days for complicated cases); a single 800 mg dose may be used for uncomplicated gonorrhoea and prostatitis is commonly treated with 400 mg every 12 hours for 4–6 weeks — doses should be adjusted for renal impairment and according to local guidelines.
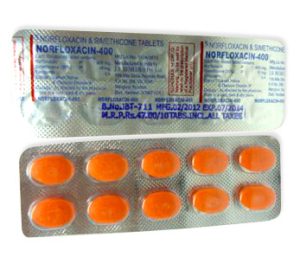
- Administered orally as a film‑coated tablet (400 mg most commonly; 200 mg less common); ophthalmic formulations exist but oral tablets are the primary form.
- Noroxin is absorbed quickly with peak blood levels around 1–2 hours after dosing; bactericidal activity begins soon after therapeutic levels are reached and some symptom improvement is often seen within 24–48 hours.
- The plasma half‑life is about 3–4 hours and the clinical effect of a dose is maintained sufficiently to allow twice‑daily dosing (approximately 12 hours); total treatment duration depends on the indication (from 3 days up to several weeks for prostatitis).
- Avoid alcohol while taking noroxin — alcohol can worsen dizziness, impair recovery and increase the chance of gastrointestinal and central nervous system side effects.
- The most common side effects are gastrointestinal upset (nausea, diarrhoea, abdominal pain), dizziness, headache and skin rash; rarer but serious effects include tendon pain or tendinitis, CNS effects and photosensitivity.
- Would you like to try “noroxin” without a prescription?
Critical Warnings & Restrictions
Basic Noroxin Information
- INN (International Nonproprietary Name): Norfloxacin
- Brand Names Available In Australia: not specified
- ATC Code: J01MA06
- Forms & Dosages: Tablet — commonly 400 mg (200 mg rare); suspension not common; ophthalmic solutions exist but not widely available.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx only in all countries per available data)
High-Risk Groups
Norfloxacin is a fluoroquinolone with recognised serious adverse effects including tendinopathy, central nervous system effects and QT prolongation.
Known hypersensitivity to norfloxacin or other quinolones is an absolute contraindication.
- Pregnant and breastfeeding people — avoid unless benefit clearly outweighs risk.
- Children and adolescents — not recommended because of arthropathy risk.
- Elderly patients — higher risk of adverse effects and drug accumulation if renal function reduced.
- People with myasthenia gravis — may exacerbate muscle weakness.
- People with seizure disorders or history of central nervous system disorders.
- Patients with known QT prolongation or taking QT‑prolonging medicines.
- Severe renal impairment — adjust dose or avoid if CrCl <30 mL/min.
Prescriber Safety Checklist
- Confirm full drug history including OTC antacids, iron, zinc and recent antibiotic courses.
- Check for allergy to quinolones or previous tendon reactions to fluoroquinolones.
- Assess renal function and calculate CrCl before starting; adjust if CrCl <30 mL/min.
- Consider ECG if patient has cardiac disease or is on other QT‑prolonging drugs.
- Confirm pregnancy status where applicable and counsel on breastfeeding risks.
- Review seizure history and consider alternative where risk present.
- Document the informed decision and advise patient to report tendon pain or CNS effects immediately.
Australian prescribers should consult TGA safety advice and local renal calculators when deciding dosing and monitoring.
Interaction With Activities (Driving, Workplace Safety)
Norfloxacin can cause central nervous system adverse effects such as dizziness, somnolence and visual disturbance which may impair driving or operation of heavy machinery.
Advise patients not to drive or operate machinery if they feel dizzy, drowsy or notice visual changes after taking the medicine.
Australian workplace law requires reporting of fitness-for-duty concerns in safety‑critical roles.
Pharmacists and employers should counsel employees in safety‑critical work about the potential for impairment and document counselling.
Q&A — “Can I Drive After Taking It In Australia?”
Avoid driving or operating heavy machinery if you feel dizzy, sleepy or have visual disturbances after taking norfloxacin.
If these symptoms occur do not drive and seek medical advice.
If you are unsure whether a side effect may affect your fitness for work, discuss with your prescriber or pharmacist before starting treatment.
Usage Basics
INN And Brand Names Relevant To Australia
People often search for brand recognition when filling prescriptions or buying overseas stock.
| INN | Typical Tablet Form | Common International Brands |
|---|---|---|
| Norfloxacin | 400 mg film-coated tablet (most frequent) | Noroxin (Merck); Norflohexal; Lexinor; Norflox; multiple generics from Torrent, Cipla, Hexal |
Availability in Australia varies by sponsor and ARTG listing, so check TGA ARTG for registered presentations and local generic brands.
Legal Classification (TGA Approval, PBS Considerations)
- Prescription-only medicine in all jurisdictions per available data.
- TGA registration status may vary by manufacturer and presentation; check the ARTG before procurement.
- Norfloxacin is not commonly first-line for uncomplicated urinary tract infection in Australian guidance, where nitrofurantoin or trimethoprim are preferred.
- PBS subsidy for norfloxacin may be limited or absent for many indications; check the current PBS Schedule for listing and authority requirements.
- Prescribers should confirm ARTG and PBS listings online prior to advising patients on subsidy or cost.
Dosing Guide
Standard Regimens
| Indication | Dose | Typical Duration |
|---|---|---|
| Uncomplicated UTI | 400 mg orally every 12 hours | 3–7 days |
| Complicated UTI / Pyelonephritis | 400 mg orally every 12 hours | 7–10 days |
| Prostatitis | 400 mg orally every 12 hours | 4–6 weeks |
| Gonorrhoea (historical use) | 800 mg single oral dose | Single dose (not first-line due to resistance) |
Table guidance reflects typical adult dosing reported internationally and should be adjusted to local susceptibility patterns and specialist advice.
Adjustments For Comorbidities
Renal impairment requires dose adjustment when CrCl is less than 30 mL/min, commonly by reducing to 400 mg once daily.
Children and adolescents are generally excluded due to risk of arthropathy and should only receive norfloxacin in exceptional situations with specialist oversight.
Elderly patients should have renal function monitored and counselled closely about side effects.
Hepatic impairment: use with caution; routine dose changes are not specified but monitor clinically.
Dose-Adjustment Checklist
- Measure or review recent CrCl before initiating treatment.
- Check interacting medicines that affect elimination or QT interval.
- If CrCl <30 mL/min, consider 400 mg once daily or specialist renal advice.
- Document rationale for alternative dosing and arrange follow-up.
Q&A — “What If I Miss A Dose?”
Take the missed dose as soon as you remember unless it is nearly time for your next dose.
Do not double up doses to make up for a missed dose.
If several doses have been missed or if symptoms worsen, contact your prescriber or pharmacist for advice.
Interaction Chart (Food, Drink & Medicines)
Food And Drinks (Alcohol, Dairy, Australian Diet Context)
Dairy and calcium-fortified foods can reduce absorption of norfloxacin by chelation.
Antacids containing aluminium or magnesium, sucralfate, and iron or zinc supplements also reduce absorption.
Advise separating these from norfloxacin by at least 2–4 hours to preserve antibiotic absorption.
Alcohol does not have a specific pharmacokinetic interaction with norfloxacin but may worsen dizziness and gastrointestinal upset.
| Food/Drink | Interaction | Practical Advice |
|---|---|---|
| Dairy, calcium-fortified milk/cereals | May chelate and reduce absorption | Take norfloxacin 2–4 hours before or after these foods |
| Antacids (Al/Mg), Sucralfate | Reduced absorption due to chelation | Separate dosing by at least 2–4 hours |
| Iron or Zinc Supplements | Reduced absorption | Separate by at least 2–4 hours |
| Alcohol | May worsen CNS or GI side effects | Avoid excessive alcohol while symptomatic |
Common Drug Conflicts
Counsel patients and check medicine lists for interactions prior to supply.
- Antacids, iron and zinc supplements — reduce norfloxacin absorption; separate dosing by 2–4 hours.
- Warfarin and other vitamin K antagonists — fluoroquinolones may potentiate anticoagulant effect; monitor INR during and after therapy.
- QT‑prolonging drugs (amiodarone, sotalol, some antipsychotics) — increased risk of torsades; consider ECG monitoring.
- Theophylline — increased theophylline levels and seizure risk reported; avoid concomitant use or monitor serum levels.
- Non‑steroidal anti‑inflammatories (NSAIDs) — may increase risk of CNS toxicity including seizures in susceptible patients.
Suggested monitoring actions include baseline ECG for QT risk, INR checks for patients on warfarin and renal function review for dose adjustments.
User Reports & Trends (Australian Patient Feedback)
Patients often report common and expected adverse effects alongside positive treatment experiences when infections respond quickly.
- Most frequent complaints on community forums are gastrointestinal upset such as nausea and diarrhoea.
- Dizziness and transient CNS effects like headache and sleep disturbance are commonly mentioned.
- Tendon pain and tendinitis are reported less frequently but are a serious concern that causes early treatment cessation in some cases.
- Positive feedback often highlights short course convenience and rapid symptom relief for some UTIs.
Anecdotal reports can over‑represent adverse events compared with pharmacovigilance data.
Encourage patients and clinicians to report suspected adverse events to the TGA Adverse Event Monitoring System to support safety surveillance.
| Reported Theme | Relative Frequency In Forums | Expected Clinical Concern |
|---|---|---|
| Gastrointestinal upset | Common | Expected; usually mild-to-moderate |
| Dizziness / CNS effects | Common | Monitor; avoid driving if affected |
| Tendon pain / rupture | Uncommon but prominent in reports | Serious; stop drug and seek urgent assessment |
Clinicians should ask about work and athletic activities because tendon injuries may affect sporting and manual occupations.
Access & Purchase Options In Australia
Major National Chains And Cost Sensitivity
Availability of norfloxacin in major chains varies with supplier and TGA registration status.
Chemist Warehouse, Priceline and TerryWhite Chemmart may stock norfloxacin when supplied by local wholesalers, but stock and brand vary.
Many Australian patients are cost‑sensitive and rely on PBS subsidies; if norfloxacin is not PBS‑listed for a given indication, a private script cost will apply.
| Pharmacy / Source | Typical Price Range (Private Script) | PBS Subsidy Status |
|---|---|---|
| Chemist Warehouse (in-store / online) | Varies by brand and pack size | Check current PBS |
| Priceline | Varies by brand and pack size | Check current PBS |
| TerryWhite Chemmart | Varies by brand and pack size | Check current PBS |
Prices and stock change; pharmacists should verify current manufacturer and PBS status before advising patients.
In our online pharmacy, noroxin is available without a prescription, with discreet delivery to Australia in 9-21 days.
Online Pharmacies, Telehealth & E-Prescriptions
Telehealth e‑prescriptions are common and allow remote consultation for urinary symptoms and repeat scripts.
Pharmacists should verify e‑prescription authenticity, confirm identity and allergies, and provide remote counselling.
Rural patients benefit from mail‑order pharmacies, but allow for delivery delays and ensure appropriate storage during transit.
Remote Dispensing Checklist
- Verify patient identity and prescription validity.
- Check allergy history and current medicines including OTC antacids and supplements.
- Provide clear counselling on dosing, interactions and when to seek urgent care.
- Confirm suitable postal conditions and advise on signature or safe drop site to avoid heat exposure.
Mechanism & Pharmacology
Simplified Explanation
Norfloxacin is a fluoroquinolone antibiotic that inhibits bacterial DNA gyrase and topoisomerase IV.
By blocking these enzymes the drug prevents bacterial DNA replication and causes bactericidal activity, especially against many Gram‑negative organisms that commonly cause urinary tract infections.
The ATC classification is J01MA06, reflecting its place in systemic fluoroquinolones.
Clinical Pharmacology Terms
| Parameter | Clinical Implication |
|---|---|
| Absorption | Oral bioavailability reduced by chelating agents (antacids, iron); separate dosing by 2–4 hours. |
| Distribution | Concentrates in the urinary tract, supporting UTI use. |
| Elimination | Primarily renal — dose adjustment needed in renal impairment. |
| Half-Life | Supports 12‑hourly dosing for 400 mg in adults. |
Indications & Off-Label Uses
Approved Indications (TGA Perspective)
Typical registered and internationally recognised indications include uncomplicated and complicated urinary tract infections, prostatitis and some gastrointestinal infections depending on jurisdiction.
Historically a single 800 mg dose was used for gonorrhoea but rising resistance limits its role and it is not commonly first‑line.
Check the TGA ARTG for specific registered indications for each sponsor and presentation in Australia.
Off-Label And Limited Uses In Australian Practice
- Traveller’s diarrhoea in combinations (some formulations abroad combine norfloxacin with tinidazole) — not common practice in Australia without culture sensitivity support.
- Limited use for specific gastrointestinal infections where culture and sensitivity demonstrate susceptibility.
- Nosocomial or complicated infections where alternative agents are unsuitable and specialist advice supports use.
Off‑label prescribing should document the rationale, obtain informed consent and align with local antimicrobial stewardship principles.
Key Clinical Findings (Evidence 2022–2026 & Safety Updates)
Regulatory reviews up to 2026 continue to emphasise rare but serious adverse events associated with fluoroquinolones including tendon rupture, persistent peripheral neuropathy, CNS effects and QT prolongation.
Resistance among Enterobacterales causing UTIs has reduced quinolone effectiveness in many regions, underlining the importance of local antibiograms.
- Safety signals: tendon injury, neuropathy and CNS events remain a concern even when uncommon.
- Resistance trends: increasing resistance in community E. coli limits empirical quinolone use for uncomplicated UTI.
- Guideline impact: many guidelines favour nitrofurantoin or trimethoprim for lower UTI where susceptibility allows.
| Regulator | Advisory Focus |
|---|---|
| EMA | Fluoroquinolone safety communications and restricted use guidance |
| FDA | Safety updates on tendon and neurological risks |
| TGA | National safety communications aligned with international regulators; subscribe to TGA alerts |
Alternatives Matrix (PBS-Listed Options & Clinical Pros/Cons)
PBS-Listed Alternatives Comparison Table
| Agent | PBS Subsidy Status | Typical Dosing | Renal Considerations | Common Adverse Effects |
|---|---|---|---|---|
| Nitrofurantoin | Commonly PBS-listed for uncomplicated UTI | Usually 100 mg twice daily or 50 mg four times daily depending on formulation | Avoid in significant renal impairment (low urine concentrations) | GI upset, pulmonary reactions (rare), peripheral neuropathy |
| Trimethoprim | Often PBS-listed | 200 mg once or twice daily depending on indication | Adjust for renal impairment; monitor blood counts | GI upset, rash, photosensitivity, haematological effects |
| Amoxicillin/Clavulanate | Often PBS-listed | 500/125 mg two or three times daily depending on infection | Dose adjust in renal impairment | GI upset, diarrhoea, allergic reactions |
| Ciprofloxacin / Levofloxacin | Available but with safety considerations similar to norfloxacin | Varies by drug and indication | Adjust for renal impairment | Fluoroquinolone-associated tendon and CNS effects, QT risk |
Pros And Cons Checklist
- Nitrofurantoin: first-line for lower UTI when the pathogen is likely susceptible; safer antimicrobial profile regarding tendon/CNS effects but limited for upper UTI.
- Trimethoprim: good oral option for lower UTI; check resistance locally and avoid in pregnancy in some trimesters.
- Beta-lactams: broader safety in some populations; variable efficacy for some Enterobacterales and may require longer courses.
- Other fluoroquinolones: similar risks to norfloxacin and should be reserved when benefits outweigh risks and susceptibility is confirmed.
Where nitrofurantoin suffices, it is often preferred over norfloxacin because of safety and resistance concerns.
Common Questions (Pharmacy Consultations & Quick Answers)
Pharmacists need concise scripts to answer patient questions and ensure safe use.
- How quickly will symptoms improve? Many patients notice symptomatic improvement within 48–72 hours, but complete the prescribed course unless advised otherwise and seek review if no improvement.
- Can I take antacids? Antacids containing aluminium or magnesium, sucralfate and iron supplements reduce absorption; separate by 2–4 hours.
- What side effects should I watch for? Stop the medicine and seek urgent care for signs of tendon pain, severe diarrhoea (possible C. difficile), new muscle weakness (myasthenia gravis) or signs of arrhythmia.
- Can I exercise / lift heavy objects? Avoid or reduce high-impact exercise if you develop tendon pain; stop the antibiotic and seek assessment if tendon discomfort begins.
Counselling Prompts
- Confirm indication and expected duration of therapy.
- Check allergies and current medicines (particularly anticoagulants, antacids and QT‑prolonging drugs).
- Confirm pregnancy and breastfeeding status.
- Assess renal function if available and ask about occupation or sports participation that may raise tendon risk.
Quick Script For Pharmacists
“This is norfloxacin 400 mg, taken twice daily for X days as prescribed.
Avoid antacids, iron or calcium-rich foods within two to four hours of each dose.
Watch for dizziness, tendon pain or signs of irregular heartbeat and stop and seek urgent review if you notice them.”
Price & Access Comparison Table
Prices fluctuate and depend on brand, pack size and PBS listing.
| Pharmacy / Source | Typical Price Range (Private Script) | PBS Subsidy Status | Prescription Requirement | Typical Turnaround |
|---|---|---|---|---|
| Chemist Warehouse | Variable by brand | Check PBS | Rx only | In-store same day; online 1–3 business days |
| Priceline | Variable by brand | Check PBS | Rx only | In-store same day; online 1–3 business days |
| Online Pharmacies (mail order) | May be lower for generics | Check PBS | Rx only | Mail 9–21 days depending on location |
Checklist of patient options: local pickup, home delivery, telehealth prescription, PBS authority scripts where applicable.
Registration & Regulation (TGA & PBS Practicalities)
TGA Approval & ARTG Checks
Always check the Australian Register of Therapeutic Goods (ARTG) for current norfloxacin registrations and sponsor details before procurement.
TGA safety communications align with international regulators and pharmacists should subscribe to TGA alerts to receive updates.
PBS Subsidy Details & Prescribing Rules
- Confirm whether norfloxacin is PBS‑listed for the intended indication and whether an authority is required.
- If subsidised, follow the PBS item number and authority form requirements when prescribing.
- Where not subsidised, advise patients on likely private script costs and cheaper alternatives where appropriate.
- Checklist for prescribers: check ARTG entry, confirm PBS code if subsidy is expected and complete authority paperwork if required.
Storage & Handling (Household & Pharmacy)
Household Storage In Australian Climate
Store norfloxacin tablets at 20–25°C, protected from moisture and light.
Advise patients not to store tablets in bathrooms where humidity is high and to avoid leaving medicine in hot cars during Australian summers.
If delivery occurs during hot weather, recommend the patient retrieve the parcel promptly and store in a cool dry place.
Emergency steps if exposed to excessive heat include checking tablet integrity, expiry date and consulting the pharmacist before use.
- Keep in original packaging to protect from moisture.
- Do not freeze tablets.
- Return unused medicines to the pharmacy for proper disposal.
Cold-Chain & Pharmacy Handling
Tablets do not require cold chain storage but should be stored per supplier instructions at 20–25°C in the dispensary.
Maintain stock rotation and check expiry dates regularly.
For any ophthalmic or other specialty presentations follow manufacturer cold‑store instructions if provided.
Guidelines For Proper Use (Australian Counselling & Official Advice)
Australian Pharmacist Counselling Style (Practical Script)
Confirm the indication, duration and dosing schedule and explain separation from antacids and supplements by 2–4 hours.
Warn about tendon pain and CNS effects and instruct the patient to stop the medicine and seek urgent care if tendon pain or muscle weakness occurs.
Advise against driving or operating heavy machinery if experiencing dizziness or visual disturbance.
Discuss interactions with warfarin and QT‑prolonging drugs and arrange INR or ECG monitoring where indicated.
Patient Advice From PBS And National Health Authorities
- Advise patients to check PBS for subsidy eligibility and inform them if a private script cost is likely.
- Encourage return of unused medicines to the pharmacy for safe disposal.
- Provide credible resources such as the TGA website and local health services for further reading and adverse event reporting.
Definitions: ARTG = Australian Register of Therapeutic Goods; PBS = Pharmaceutical Benefits Scheme; CrCl = creatinine clearance.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9-14 days |
| Melbourne | Victoria | 9-14 days |
| Brisbane | Queensland | 9-14 days |
| Perth | Western Australia | 9-14 days |
| Adelaide | South Australia | 9-14 days |
| Hobart | Tasmania | 9-14 days |
| Canberra | Australian Capital Territory | 9-14 days |
| Darwin | Northern Territory | 14-21 days |
| Townsville | Queensland | 14-21 days |
| Geelong | Victoria | 14-21 days |
| Newcastle | New South Wales | 14-21 days |
| Wollongong | New South Wales | 14-21 days |
| Sunshine Coast | Queensland | 14-21 days |
| Albury | New South Wales / Victoria | 14-21 days |
Final Notes And Practical Tips
Keep clear records of counselling, renal function and any monitoring required when supplying norfloxacin or advising about noroxin 400 mg tablets.
Report suspected adverse events to the TGA to support national pharmacovigilance.
If norfloxacin is considered, ensure culture and sensitivity where possible and prefer narrower spectrum or safer PBS‑listed alternatives when appropriate.
Contact the pharmacy for questions about interactions, dosing adjustments or delivery options.