Toprol Xl
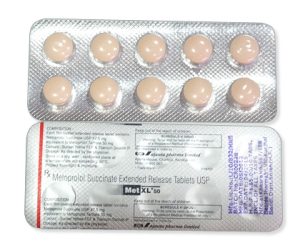
In brief
- Toprol XL is a prescription medicine in most countries (including Australia) and is usually dispensed from pharmacies with a prescription; however, some pharmacies or online sellers may offer it without requiring a receipt—this is not recommended and you should consult a prescriber before use.
- Toprol XL (metoprolol succinate) is used for hypertension, angina, heart failure and post‑myocardial infarction care; it is a selective beta‑1 adrenergic receptor antagonist (beta‑blocker) that reduces heart rate and cardiac workload.
- Usual doses vary by indication: hypertension 25–100 mg once daily (maintenance commonly 100–200 mg once daily); angina 100 mg once daily (up to 200 mg); heart failure start 12.5–25 mg once daily and titrate up to 200 mg once daily; post‑MI typically 100–200 mg once daily.
- Administered orally as extended‑release tablets or capsules (Toprol XL ER formulations 25, 50, 100, 200 mg); immediate‑release metoprolol (tartrate) is a different product taken more frequently. Take Toprol XL with or shortly after a meal to improve absorption.
- Effects on heart rate and blood pressure begin within 1–2 hours after an extended‑release dose, though full therapeutic benefits for blood pressure or angina control may take days to weeks as dose is titrated.
- Toprol XL is formulated for once‑daily dosing with a duration of effect of about 24 hours when taken as directed (extended‑release formulation provides sustained plasma levels over the day).
- Avoid excessive alcohol while taking Toprol XL; alcohol can increase drowsiness, worsen blood‑pressure lowering and lightheadedness, and may exacerbate side effects like dizziness or fainting.
- The most common side effect is fatigue (tiredness); other frequent effects include dizziness, sleep disturbances and slow heart rate (bradycardia).
- Would you like to try “toprol xl” without a prescription?
Critical Warnings & Restrictions (Safety First) — Patient Protection For Australia
Basic Toprol Xl Information
- INN (International Nonproprietary Name): Metoprolol succinate.
- Brand Names Available In Australia: not specified.
- ATC Code: C07AB02 — Selective beta-blocker, beta-1 adrenergic receptor antagonist.
- Forms & Dosages: Extended-release tablets 25 mg, 50 mg, 100 mg, 200 mg; capsule extended-release common in North America; immediate-release metoprolol tartrate available as separate products (e.g., Lopressor).
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx).
High-Risk Groups (Elderly, Pregnancy, Chronic Illness)
Who needs extra screening before supply?
- Absolute contraindications: severe bradycardia (<45 bpm); second- or third-degree heart block without a pacemaker; sick sinus syndrome; uncompensated heart failure or cardiogenic shock; severe peripheral arterial circulatory disorders; known hypersensitivity to metoprolol or excipients.
- Use extreme caution in the elderly: start at the low end of dosing and monitor for bradycardia and hypotension.
- Pregnancy: category C — use only if benefit justifies risk to the fetus and after discussion with the prescriber.
- Chronic lung disease: asthma or COPD may worsen due to beta-blockade; consider specialist advice.
- Diabetes: beta-blockers can mask hypoglycaemia signs such as tremor and tachycardia — increase glucose monitoring.
- Thyroid disease: may mask signs of thyrotoxicosis and alter clinical picture.
- Psoriasis and hepatic impairment: may exacerbate symptoms or need dose adjustment due to hepatic metabolism.
Screening checklist Before Dispensing:
- Measure baseline blood pressure and heart rate.
- Review current medications and perform medication reconciliation to avoid inadvertent switch from metoprolol tartrate (immediate-release) to succinate (extended-release) or vice versa without prescriber approval.
- Obtain ECG if there is suspected conduction disease or history of syncope, bradycardia, or heart block.
- Assess liver function tests where hepatic impairment is suspected.
- Document a titration and monitoring plan in the patient record.
Interaction With Activities (Driving, Workplace Safety Under Australian Law)
Many people ask whether metoprolol affects daily tasks like driving or operating machinery.
Q&A — “Can I Drive After Taking It In Australia?”
Metoprolol may cause dizziness, fatigue or blurred vision, particularly when treatment starts or dose changes occur.
If a patient feels unsteady, drowsy or light-headed they must not drive or operate heavy machinery.
This advice aligns with Australian road rules and workplace safety obligations for safety-critical roles.
Counselling point: avoid driving until dose effects are known, especially when starting therapy or after dose adjustments.
Employers and safety-critical workers should discuss fitness for work with the treating clinician and follow any required reporting procedures.
Safe To Drive? Checklist:
- No dizziness or light-headedness at rest or on standing.
- Heart rate is stable and not unusually slow after starting or increasing dose.
- No recent dose change within the last 48–72 hours without verified tolerance.
Usage Basics
INN, Brand Names Available In Australia
What Is The Drug Called?
The international nonproprietary name is metoprolol succinate.
Common international brands include Toprol XL and branded generics; local Australian brands are not specified in the raw data so check ARTG entries or pharmacy stock.
Important Distinction:
- Metoprolol Succinate (Extended-Release)
- Once-daily controlled-release tablet intended for steady 24-hour effect.
- Metoprolol Tartrate (Immediate-Release)
- Shorter-acting formulation often dosed twice daily; branded as Lopressor in some markets and not interchangeable with succinate for chronic therapy.
Available Extended-Release Strengths Internationally: 25 mg, 50 mg, 100 mg, 200 mg.
Legal Classification (TGA-Approved, PBS-Listed)
Metoprolol succinate and Toprol XL are prescription-only products in all markets according to the product data.
In Australia pharmacists should confirm the specific product entry on the TGA ARTG and check PBS listings to determine subsidy, authority requirements and any brand restrictions.
When counselling patients, verify e-prescription validity and confirm patient consent for electronic transmission.
Suggested Table For Pharmacy Use:
- TGA ARTG entry — record product sponsor and ARTG number when dispensing.
- PBS listing — check for subsidy, authority requirements and preferred brands.
- Prescription requirement — prescription-only; confirm legitimacy of the script.
- Subsidy details — discuss likely out-of-pocket cost versus PBS-subsidised price where applicable.
Dosing Guide
Standard Regimens (PBS Reference Dosing)
Typical Dosing By Indication:
| Indication | Initial Dose | Typical Maintenance | Maximum |
|---|---|---|---|
| Hypertension (Adults) | 25–100 mg once daily | 100–200 mg once daily | 200 mg once daily |
| Angina Pectoris | 100 mg once daily | 100–200 mg once daily | 200 mg once daily |
| Heart Failure | 12.5–25 mg once daily | Titrate up to 200 mg once daily as tolerated | 200 mg once daily |
| Post-Myocardial Infarction | 100 mg once daily | 100–200 mg once daily | 200 mg once daily |
Checklist For Titration Steps:
- Start at the low end for elderly patients or those with comorbidities.
- Allow several days between dose increases while monitoring HR and BP.
- Document heart rate and blood pressure at each step and report symptomatic bradycardia or hypotension immediately.
Adjustments For Comorbidities
How To Adjust Doses For Specific Patients.
- Elderly: start low and monitor closely for bradycardia and orthostatic hypotension.
- Liver Impairment: consider dose reduction because metoprolol is hepatically metabolised.
- Renal Impairment: usually no adjustment required, but monitor at higher doses.
- Pediatric: off-label and should only be used under specialist supervision with individualised dosing.
- Diabetes: warn that beta-blockers may mask hypoglycaemia signs; advise more frequent glucose checks and carry hypoglycaemia action plan.
Q&A — “What If I Miss A Dose?”
If a dose is remembered soon after the usual time take it immediately.
If it is almost time for the next dose skip the missed dose and resume the regular schedule.
Do not double up doses to make up for missed doses.
Seek pharmacist or prescriber advice if multiple doses have been missed or if vomiting prevents oral absorption.
Interaction Chart
Food And Drinks (Alcohol, Coffee, Australian Diet Context)
Alcohol can intensify drowsiness and orthostatic hypotension when combined with metoprolol.
Advise patients to moderate alcohol intake and avoid heavy drinking while stabilising on therapy.
Caffeine does not cause clinically important pharmacokinetic interactions with metoprolol but can mask fatigue and interfere with sleep.
Typical Australian dietary sources worth mentioning include coffee, energy drinks and high-caffeine soft drinks.
Administration Advice: take metoprolol with or immediately after meals to improve absorption and reduce gastrointestinal side effects.
Dietary Advice Bullet Points:
- Limit alcohol until you know how metoprolol affects you.
- Be cautious with energy drinks and excessive coffee if you notice jitteriness or palpitations.
- Take the tablet after food to improve tolerability.
“Avoid If Symptomatic” Checklist:
- Avoid alcohol if feeling light-headed or excessively drowsy.
- See a clinician if you develop persistent dizziness or syncope after combining substances.
Common Drug Conflicts
Major interactions to screen for when dispensing metoprolol succinate.
| Drug | Interaction Type | Action |
|---|---|---|
| Verapamil, Diltiazem | Increased risk of bradycardia and AV block | Consult prescriber; avoid combination unless monitored closely; consider ECG monitoring. |
| Digitalis (Digoxin) | Additive bradycardia | Monitor heart rate and ECG; adjust doses if necessary. |
| Other Antihypertensives | Enhanced hypotensive effect | Review combination therapy; monitor BP closely. |
| MAO Inhibitors, Some Antidepressants | Altered autonomic responses or potentiation of effects | Pharmacist should review therapy and liaise with prescriber. |
Severity Definitions:
- Major — combination may cause serious harm; avoid or require specialist supervision.
- Moderate — adjust dose and monitor more frequently.
- Minor — counselling and routine monitoring sufficient.
User Reports & Trends (Australian Patient Feedback)
What Patients Often Say In Australia.
- Initial tiredness and fatigue are commonly reported during the first 1–2 weeks of treatment or during titration.
- Dizziness on standing is a frequent short-term complaint that often resolves with dose adjustment.
- Many patients report good long-term blood pressure and angina control once the dose is stabilised.
- Supply switching between branded Toprol XL and generic metoprolol succinate ER can lead to perceived efficacy differences; medication reconciliation is important.
- Some patients notice sleep disturbances or vivid dreams, which may need a change in therapy.
Pharmacist Checklist To Capture Patient Experience:
- Ask about sleep, daytime energy and dizziness since starting the medication.
- Check heart rate at rest and orthostatic blood pressure where feasible.
- Record any perceived change after switching brands and liaise with prescriber if adherence or efficacy concerns arise.
- Report suspected adverse events to the TGA via the Adverse Event Reporting system.
Access & Purchase Options (Australia)
National Chains (Chemist Warehouse, Priceline, TerryWhite Chemmart)
Metoprolol succinate ER is a prescription-only medicine and major chains dispense branded Toprol XL and generics where stocked.
Price sensitivity is common and PBS subsidy, where applicable, often determines the out-of-pocket cost.
Pharmacists should confirm ARTG sponsorship and generic availability before advising on likely patient cost.
Typical Store Advice:
- Phone ahead to confirm stock and strengths (25/50/100/200 mg) at your local branch.
- Discuss PBS entitlement or private pricing and whether an authority script is required for subsidy.
- Record brand dispensed for continuity of care.
Online Pharmacies And Telehealth E-Prescriptions
Australian online pharmacies and telehealth providers can supply metoprolol following a valid prescription in line with regulations.
Verify e-prescription validity and patient identity before dispatch.
Caution rural and remote patients about postal delays and advise keeping a one- to two-week buffer for essential cardiovascular medicines.
Online Purchase Checklist:
- Valid prescription from an authorised prescriber is required before dispensing.
- Use a TGA-registered pharmacy and confirm ARTG/sponsor details when in doubt.
- Ensure packaging protects tablets from heat and humidity during transit.
Note: our online pharmacy can dispense metoprolol succinate with a valid prescription and offers discreet delivery across Australia in 9–21 days.
Mechanism & Pharmacology
Simplified Explanation
How Metoprolol Works.
Metoprolol succinate is a selective beta-1 adrenergic receptor antagonist that reduces heart rate and myocardial contractility.
Lowered heart rate and contractility reduce myocardial oxygen demand and contribute to blood pressure reduction and angina control.
The succinate salt provides an extended-release formulation for once-daily dosing and more even 24-hour plasma levels compared with immediate-release tartrate.
Patient Leaflet Suggestions:
- Simple diagram showing “Beta-1 Blockade → Slower Heart Rate → Lower Blood Pressure/Reduced Chest Pain”.
- Explain once-daily ER purpose: steadier effect and improved adherence.
Clinical Terms
Key Pharmacology Terms Patients Should Know.
- Steady-State — when blood levels are consistent after repeated dosing.
- Titration — starting at a low dose and slowly increasing to a tolerated or effective dose.
- Bradycardia — abnormally slow heart rate that may require dose adjustment or cessation.
- CYP2D6 Variability — genetic differences in metabolism that can change metoprolol levels in some patients.
Pharmacokinetics Notes: hepatic metabolism predominates so dose adjustments are likely in significant liver disease.
Pharmacodynamics Notes: ER formulations provide a slower onset and smoother peak-to-trough control over 24 hours.
Indications & Off-Label Uses
Approved Indications By TGA
International approvals list hypertension, angina pectoris, heart failure and post-myocardial infarction use as common indications.
Australian prescribing should mirror the TGA-approved product information as per the ARTG; check product registration details for exact indications.
Indication Table (Typical Dosing):
| Indication | Typical Starting Dose | Maintenance |
|---|---|---|
| Hypertension | 25–100 mg once daily | 100–200 mg once daily |
| Angina | 100 mg once daily | Up to 200 mg once daily |
| Heart Failure | 12.5–25 mg once daily | Titrate to 200 mg once daily |
| Post-MI | 100 mg once daily | 100–200 mg once daily |
Off-Label Uses In Australian Clinical Practice
Some off-label uses occur under specialist guidance.
- Performance anxiety or situational anxiety in selected patients, often with short-term use.
- Migraine prophylaxis in select adult patients under clinician supervision.
- Certain arrhythmias for rate control when recommended by a cardiologist.
- Pediatric use is off-label and requires specialist oversight and dose individualisation.
Referral Checklist:
- Refer to cardiology for complex heart failure or arrhythmia management.
- Refer to paediatrics for any child or adolescent requiring beta-blocker therapy.
Key Clinical Findings (Australian & International Studies 2022–2026)
What Recent Evidence Emphasises.
- Beta-blockers provide mortality benefit post-myocardial infarction and remain part of secondary prevention strategies.
- Careful titration in heart failure reduces morbidity and improves symptoms when tolerated.
- Personalised dosing and consideration of multimorbidity are increasingly important given competing risks and new antihypertensive classes.
Evidence Priorities For Clinicians:
- Mortality benefit post-MI supports continued use unless contraindicated.
- Symptomatic angina control is a well-established indication.
- For hypertension, consider patient comorbidities and guideline recommendations when selecting beta-blockers versus other classes.
For precise guideline grades and citations consult RACGP, cardiology society statements and TGA product information.
Alternatives Matrix
PBS-Listed Alternatives Comparison Table
| Drug | Typical Indications | Dosing Frequency | PBS Status | Pros & Cons |
|---|---|---|---|---|
| Metoprolol Succinate (Toprol XL) | Hypertension, Angina, Heart Failure, Post-MI | Once daily | Check PBS listing for product-specific subsidy | ER improves adherence; hepatic metabolism; may mask hypoglycaemia. |
| Atenolol | Hypertension, Angina | Once daily | PBS-listed for some indications | Renally excreted; less lipophilic; fewer CNS effects. |
| Bisoprolol | Hypertension, Chronic Heart Failure | Once daily | PBS-listed for CHF and other indications | Strong CHF evidence; once-daily dosing; may be preferred in heart failure. |
| Carvedilol | CHF, Hypertension | Twice daily | PBS-listed for certain indications | Alpha and beta blockade useful in CHF; may cause more hypotension. |
| Nebivolol | Hypertension | Once daily | Check PBS listings | Vasodilatory properties; newer agent with differing side-effect profile. |
Pros And Cons Checklist
- Pros: Effective for rate control and angina; once-daily ER improves adherence.
- Pros: Longstanding evidence for secondary prevention after MI and for heart failure when titrated appropriately.
- Cons: May mask hypoglycaemia and provoke bronchospasm in susceptible patients.
- Cons: Hepatic metabolism means dose adjustment may be needed in liver disease.
- Cons: Do not substitute ER succinate for immediate-release tartrate formulations without prescriber approval.
Common Questions (Australian Pharmacy Consultations)
Answers To The Questions Patients Ask Most Often.
- Is This The Same As Lopressor? No — Lopressor is metoprolol tartrate (immediate-release) and is not interchangeable with metoprolol succinate (Toprol XL) for chronic therapy without clinician approval.
- Will It Affect My Diabetes? It can mask signs of hypoglycaemia such as tremor and tachycardia; maintain regular glucose monitoring and discuss with your diabetes team.
- Can I Stop It Abruptly? No — abrupt cessation can cause rebound tachycardia or angina; taper under clinical supervision.
Short Patient Script For Pharmacists:
- “This medicine is metoprolol succinate, an extended-release beta-blocker taken once daily after food.”
- “Do not stop it suddenly; if you have dizziness, very slow heart rate or breathlessness contact your prescriber.”
- “If you have diabetes, please monitor glucose more often and keep this medication on your record.”
- “Report suspected side effects to the TGA and return for review if symptoms are persistent.”
Price & Access Comparison
Comparison Table — Pharmacy/Source, Typical Price Range, PBS Subsidy Status, Prescription Required
| Supplier | Brand Vs Generic | Typical Price (Private) | PBS Subsidy | Prescription Required |
|---|---|---|---|---|
| Chemist Chains (e.g., Chemist Warehouse) | Branded and generics where stocked | Varies by brand; check local store | Depends on ARTG/PBS listing for the specific product | Yes |
| Community Pharmacies (e.g., Priceline, TerryWhite) | Branded and generics | Varies by stock | Depends on PBS listing | Yes |
| Online Pharmacies | Branded and generics | Often similar to in-store private prices | Check PBS rules for online dispensing and subsidies | Yes, valid prescription required |
Note: Toprol XL and generics are available internationally in 25–200 mg ER strengths; local pricing and PBS listing vary so verify with the dispensing pharmacy.
Access Checklist — Major Chains, Online Pharmacies, Rural Vs Urban Availability
- Confirm ARTG and PBS listing for the exact product and strength before advising on subsidy and cost.
- Phone ahead to check stock and whether a specific brand is available.
- Consider substitution permissions and document brand changes in the patient record.
- Advise rural patients to keep a 1–2 week buffer for essential cardiovascular medicines to allow for mail delays.
- Arrange PBS authority scripts where indicated to avoid gaps in supply.
Registration & Regulation
TGA Approval
Pharmacists and clinicians must verify the specific metoprolol succinate product entry on the TGA ARTG before supply.
FDA and EMA approvals exist internationally, but ARTG entries determine legal supply and sponsor for Australia.
Checklist For Verifying ARTG Listing:
- Search the TGA ARTG for product name and sponsor.
- Record the ARTG number and sponsor when dispensing for audit trail.
- Confirm approved indications and presentation match the prescription.
PBS Subsidy Details
PBS subsidy and authority requirements depend on the registered product and indication.
Pharmacists should consult the PBS Schedule for current listings and advise patients about concession pricing, safety-net thresholds and generic alternatives.
Suggested Table For Pharmacy Use: map common strengths and PBS codes to help dispensing staff locate subsidy information quickly.
Storage & Handling
Household Storage In Australian Climate (Heat/Humidity)
Store tablets at room temperature, approximately 20–25°C, away from direct light and moisture.
Keep medication in the original packaging to protect from humidity, especially in humid or hot parts of Australia.
Avoid storing medication in cars, bathrooms or uncooled sheds during summer months.
For blister packs, keep strips intact until use.
Household Storage Tips:
- Store in a cool, dry cupboard out of reach of children.
- Check expiry dates and discard expired product safely.
- If tablets have been exposed to extreme heat or moisture, consult the pharmacist before continuing use.
Cold-Chain Handling For Pharmacies
Metoprolol does not require cold-chain handling and standard ambient pharmacy storage is adequate.
Maintain proper stock rotation (first-expiry-first-out) and monitor expiry dates.
Ensure secure dispensing procedures for chronic cardiac medicines to avoid supply interruptions.
Pharmacy SOP Checklist:
- Store at room temperature away from heat sources.
- Document stock received and supplier details for traceability.
- Communicate with prescribers if supply issues arise.
Guidelines For Proper Use (Pharmacist Counselling & Patient Advice)
Australian Pharmacist Counselling Style
Use a clear, conversational tone and confirm the patient’s understanding.
Key counselling points include confirming the indication, reviewing contraindications and medication history, and measuring baseline vitals where possible.
Discuss expected side-effects such as fatigue, dizziness and slow heart rate, and explain actions for missed doses and suspected overdose.
Warn about interactions with calcium channel blockers, digitalis and some antidepressants, and stress taking the tablet with or after meals to aid absorption.
Counselling Checklist:
- Confirm why the patient was prescribed metoprolol succinate and how to take it.
- Measure or record baseline BP and HR if available and document.
- Advise on driving and workplace safety as appropriate.
- Provide a written card or sticker with the brand and strength dispensed.
Telephone Script Example For Remote Counselling:
- “This is metoprolol succinate extended-release, take once daily after food.”
- “If you feel light-headed, very tired or your pulse is very slow, contact your prescriber.”
- “Keep a record of your blood pressure and pulse for review during the first weeks of therapy.”
Patient Advice From PBS And National Health Authorities
Advise patients to report adverse events to the TGA and to keep an up-to-date medication list including over-the-counter products.
Encourage carrying emergency contact information if they have significant cardiac disease.
Never stop beta-blockers abruptly without clinician direction due to the risk of rebound symptoms.
Printable Take-Home Checklist For Patients:
- Vitals Log — record BP and HR for the first 2–4 weeks or after dose changes.
- Symptom Diary — note dizziness, breathlessness, sleep changes or excessive fatigue.
- Medication Reconciliation Note — list all current medicines and any recent brand changes.
- How To Report Side Effects — instruct to use the TGA Adverse Event reporting pathway.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 9–14 days |
| Melbourne | Victoria | 9–14 days |
| Brisbane | Queensland | 9–14 days |
| Perth | Western Australia | 9–14 days |
| Adelaide | South Australia | 9–14 days |
| Gold Coast | Queensland | 9–14 days |
| Newcastle | New South Wales | 9–14 days |
| Canberra | Australian Capital Territory | 9–14 days |
| Wollongong | New South Wales | 9–14 days |
| Sunshine Coast | Queensland | 9–14 days |
| Hobart | Tasmania | 14–21 days |
| Geelong | Victoria | 9–14 days |
| Townsville | Queensland | 14–21 days |
| Cairns | Queensland | 14–21 days |